
The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
An enclomiphene cycle is a supervised course of enclomiphene citrate, a selective estrogen receptor modulator (SERM) prescribed for men with secondary hypogonadism whose testosterone has declined. Unlike testosterone replacement therapy, enclomiphene for low testosterone works by stimulating the body's own hormone-signaling axis rather than replacing testosterone from outside. A licensed provider determines whether this approach is appropriate after reviewing bloodwork and intake, then monitors response throughout the cycle. The testes remain active, and fertility is preserved.
How enclomiphene stimulates testosterone

Testosterone production depends on a three-part feedback loop. The hypothalamus releases gonadotropin-releasing hormone (GnRH). That signals the pituitary to secrete luteinizing hormone (LH) and follicle-stimulating hormone (FSH). LH drives the testes to produce testosterone; FSH supports sperm production.
The loop has a built-in shutoff. When testosterone and the estrogen converted from it rise, they signal the hypothalamus to pull back. This keeps levels in range. When that signaling chain breaks down, testosterone falls even though the testes themselves remain capable of production. That specific failure is secondary hypogonadism: the axis misfires, not the testes.
Enclomiphene blocks estrogen receptors in the hypothalamus, interrupting the shutoff signal. The hypothalamus and pituitary keep releasing GnRH, LH, and FSH. A 2016 review by Rodriguez et al. in Expert Opinion on Pharmacotherapy found that enclomiphene raises testosterone while preserving gonadotropin levels. That is the core difference from TRT: exogenous testosterone suppresses LH and FSH, while enclomiphene amplifies the body's own production signal. This mechanism defines what makes a well-structured enclomiphene cycle effective for men with secondary hypogonadism.
Enclomiphene is the trans-isomer of clomiphene citrate. Standard clomiphene contains both the trans (enclomiphene) and cis (zuclomiphene) isomers. The cis component carries weak estrogenic properties and a longer half-life, which may contribute to side effects reported with clomiphene in men. Isolating the trans-isomer removes that estrogenic activity, producing a cleaner pharmacological profile for an enclomiphene testosterone therapy course.
For a full breakdown of how enclomiphene works as a SERM, including the isomeric distinction from clomiphene, our clinical overview covers the mechanism in detail.
What a supervised enclomiphene cycle involves
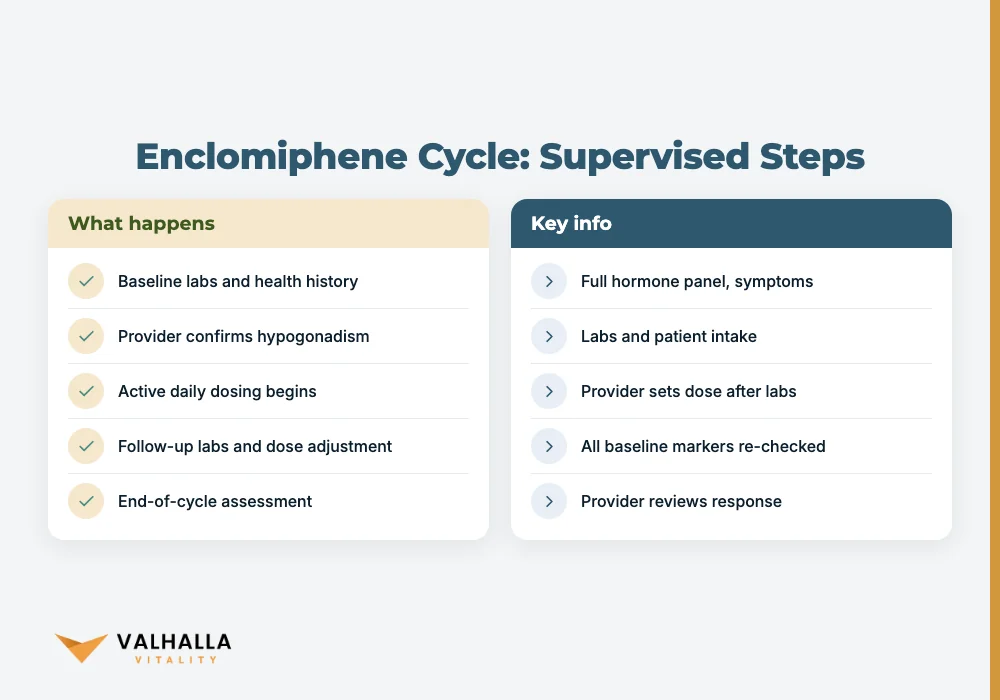
A provider-led enclomiphene cycle moves through distinct phases. Each phase depends on information from the previous one, not on a predetermined schedule.
The assessment phase begins with a full hormone panel. Labs measure total testosterone, free testosterone, LH, FSH, estradiol, and prolactin. These baseline values tell the provider whether secondary hypogonadism is present and how significant the deficit is.
A detailed health history follows, covering prior conditions, current medications, and lifestyle factors that may independently affect the hormone axis. Symptoms that prompt men to seek evaluation often include persistent fatigue, reduced libido, mood changes, and diminished erectile function. Documenting these at baseline gives the provider a reference point for tracking treatment response.
For men where fertility matters, a semen analysis at baseline captures sperm count, motility, and morphology before treatment begins.
Once secondary hypogonadism is confirmed, the provider writes the enclomiphene dosage protocol. This specifies dose and follow-up timeline. A licensed provider sets the dose after reviewing labs, not before. Adjustments occur based on follow-up bloodwork, not symptom reports alone.
| Phase | What happens | Key biomarkers |
|---|---|---|
| Baseline labs | Full hormone panel, health history, physical exam if needed | Total T, free T, LH, FSH, estradiol, prolactin |
| Provider review | Confirms secondary hypogonadism; rules out contraindications | Labs + intake |
| Active dosing | Daily enclomiphene citrate; dose set by provider after labs | Provider-determined |
| Follow-up labs | Panel re-checked; dose adjusted if indicated | All baseline markers |
| End-of-cycle assessment | Response reviewed; continuation or stop decided | Provider |
Our guide on enclomiphene dosage and how a provider sets your protocol explains how the titration process works in practice.
Enclomiphene testosterone therapy vs. TRT: what the evidence shows
The comparison matters for choosing the right approach.
TRT delivers testosterone directly. Levels rise reliably. But exogenous testosterone suppresses the pituitary's output of LH and FSH. The testes receive no signal and gradually become less active. Over time, this pattern is associated with testicular atrophy and reduced sperm production. For men unconcerned with fertility, TRT remains an effective and well-studied option.
Enclomiphene testosterone therapy takes the opposite approach. It stimulates the body's own axis rather than replacing the end product. LH and FSH remain elevated. The testes continue functioning. The 2025 systematic review and meta-analysis by Hohl et al. in Archives of Endocrinology and Metabolism analyzed multiple randomized controlled trials and found that enclomiphene raised testosterone in men with secondary hypogonadism at levels comparable to clomiphene, with acceptable tolerability.
An enclomiphene cycle prioritizes axis preservation over peak testosterone output. Men who prioritize fertility, testicular function, or avoiding long-term axis suppression may find an enclomiphene cycle more appropriate than TRT. That decision belongs to the provider after reviewing labs, goals, and health history.
Availability varies by state. To understand how the intake and prescribing process works at Valhalla Vitality, reviewing the service structure before booking is a reasonable first step.
Does enclomiphene need to be cycled?
Cycling enclomiphene is not always required. The structure of enclomiphene cycling depends on the clinical picture: the diagnosis, the therapeutic goal, and how the axis responds.
For men with secondary hypogonadism who need ongoing testosterone support, continuous enclomiphene use under regular monitoring is a valid approach. The provider checks labs at regular intervals and adjusts the protocol as values shift. This mirrors how most hormone therapies are managed over time.
Defined cycling becomes more relevant in two situations. First, when the therapeutic goal is time-limited, such as axis recovery after exogenous androgen use or a fertility-focused course before a planned conception attempt. Second, when the provider wants to assess whether the axis can sustain adequate testosterone independently after a period of stimulation. A treatment break followed by labs confirms what happens without ongoing enclomiphene support.
The decision to cycle versus continue is provider-directed. It follows from bloodwork and the treatment goal, not a fixed protocol applied to everyone. Self-directed cycling enclomiphene without lab monitoring does not replicate a supervised enclomiphene cycle. Without monitoring, there is no clinical confirmation the therapy is working.
How long should an enclomiphene cycle last?
There is no single answer. Most clinical protocols in the published literature range from several weeks to a few months.
The 2025 systematic review by Hohl et al. analyzed data from multiple randomized controlled trials comparing enclomiphene and clomiphene in men with secondary hypogonadism. Study durations varied across the trials. That variation reflects clinical reality: cycle length should match the therapeutic goal and the individual's axis response, not a fixed number.
Short courses help confirm the axis responds before committing to longer treatment. A rise in LH, FSH, and testosterone in early follow-up labs confirms the mechanism is working. If levels don't move, the provider reassesses.
Extended protocols support men who need sustained testosterone restoration. Relevant factors include the severity of the initial hormone deficit, the speed and magnitude of the hormonal response, side effects if any arise, and the end goal, whether that is testosterone restoration, fertility support, or post-cycle axis recovery.
Can you take enclomiphene on a steroid cycle?
This question reflects a distinct use case from the medically supervised enclomiphene cycle for secondary hypogonadism.
The phrases "enclomiphene on cycle" and "enclomiphene during cycle" typically surface in two scenarios: using enclomiphene alongside anabolic steroids to limit axis suppression, or using it after anabolic steroids have cleared as part of post-cycle therapy (PCT).
Anabolic steroids suppress the hypothalamic-pituitary-testicular axis by delivering exogenous androgens that signal the hypothalamus to reduce GnRH output. The pituitary follows, cutting LH and FSH. The testes receive no signal. Testosterone production falls. The degree of suppression depends on the specific compounds used, the dose, and how long the steroid cycle runs.
Using enclomiphene on cycle, during active anabolic steroid use, has limited practical effect on endogenous testosterone. The exogenous androgens dominate the feedback signal regardless of estrogen-receptor blockade at the hypothalamus. The testes stay suppressed because the androgen saturation overrides any gonadotropin stimulus.
Enclomiphene as PCT is a different situation. Once anabolic steroids have cleared, the axis needs a restart signal. Enclomiphene blocks the hypothalamic estrogen receptors, drives LH and FSH output, and stimulates testicular recovery. For a structured protocol overview, see our guide on enclomiphene as post-cycle therapy.
Any enclomiphene course, including post-cycle use, should be reviewed by a licensed provider. Labs before and after confirm whether the axis has recovered and whether additional support is needed.
What happens when you stop taking enclomiphene?
When enclomiphene is discontinued, the estrogen-receptor blockade at the hypothalamus ends. The negative feedback loop gradually resumes. For most men with secondary hypogonadism, testosterone levels return toward the pre-treatment baseline over the following weeks.
This is not the same dynamic as stopping TRT. Enclomiphene stimulated the testes throughout treatment. They remain functional when the medication ends. The axis rebalances as the hypothalamus begins responding to circulating estrogen again, which typically produces a gradual decline rather than an abrupt drop.
How quickly testosterone drifts back depends on the individual's baseline axis sensitivity and how long treatment ran. Some men see sustained improvement after a defined course. This is more likely when underlying contributors to low testosterone, such as excess body weight, disrupted sleep, or metabolic dysfunction, have also been addressed during treatment. When those factors improve, the axis may sustain better function on its own after cycling enclomiphene ends.
If follow-up labs show testosterone has returned to pre-treatment levels and symptoms have recurred, the provider uses that data to adjust the approach, whether that means a longer course, a different protocol, or closer attention to contributing factors.
Is enclomiphene safe for long-term use?
The published evidence is generally reassuring for the trial periods studied. The 2025 meta-analysis by Hohl et al. in Archives of Endocrinology and Metabolism, analyzing multiple randomized controlled trials of enclomiphene and clomiphene in men with secondary hypogonadism, found acceptable tolerability across the study durations reviewed.
Side effects are mild in most cases. Hot flashes, mood changes, and headaches are the most commonly noted. These appeared in the original clinical studies and were replicated across subsequent trials. For a detailed review of enclomiphene side effects and what to watch for, our safety overview covers what the data shows.
Long-term data beyond the current trial durations is still accumulating. The 2016 review by Rodriguez et al. in Expert Opinion on Pharmacotherapy positioned enclomiphene favorably for secondary hypogonadism, citing its cleaner isomeric profile compared to standard clomiphene. Whether that translates to a meaningfully different safety profile over years of continuous use is a question ongoing research is still addressing.
Providers manage the long-term picture through regular monitoring. Extended enclomiphene use requires lab checks at set intervals throughout the enclomiphene cycle. If any marker drifts outside the target range, the protocol is adjusted. Extended treatment without monitoring is not standard clinical practice.
Lab work and monitoring throughout the enclomiphene cycle
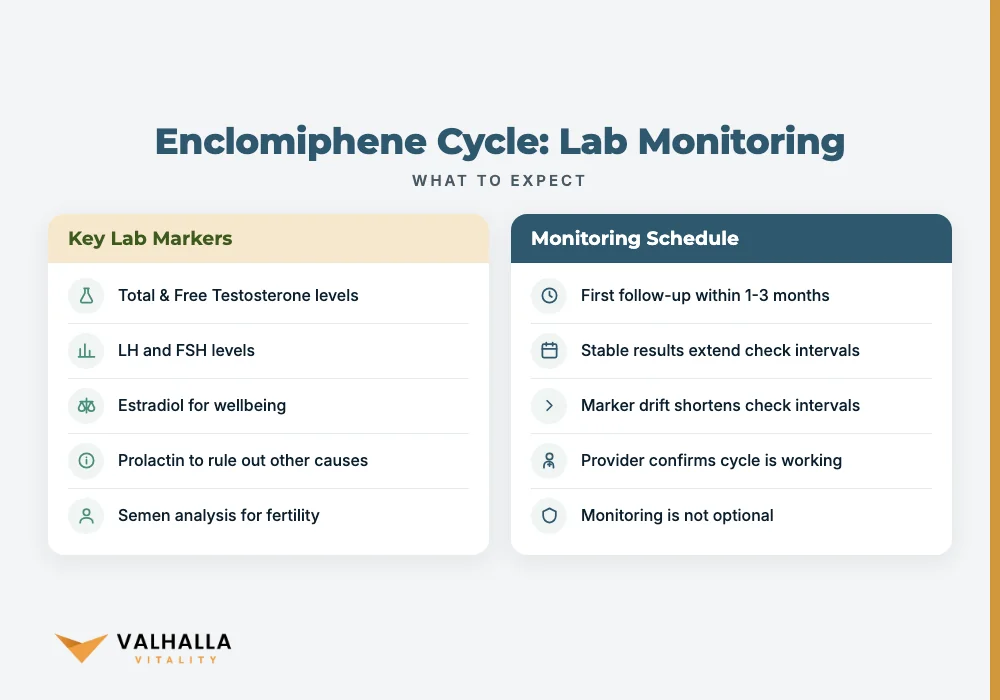
Monitoring is not optional. It is how the provider confirms the enclomiphene cycle is working as intended.
The standard monitoring panel is what makes an enclomiphene cycle medically supervised rather than self-directed. It includes:
- Total testosterone and free testosterone: the primary markers. Rising levels confirm the axis is responding to treatment.
- LH and FSH: these should rise alongside testosterone. If they do not, the mechanism may not be working as expected and the provider reassesses.
- Estradiol: enclomiphene affects estrogen metabolism as a result of receptor blockade. Monitoring keeps estradiol in a range that supports wellbeing.
- Prolactin: elevated prolactin suppresses gonadotropins. Checking at baseline and follow-up rules out a secondary cause of low testosterone that would need separate attention.
Most providers run the first follow-up panel within the first one to three months of an active enclomiphene cycle. Stable results extend the interval between checks. A drift in any marker shortens it.
For men where fertility is a treatment goal, semen analysis at baseline and at follow-up tracks changes in sperm parameters. A 2016 review by Rodriguez et al. in Expert Opinion on Pharmacotherapy noted that enclomiphene preserves the gonadotropin signaling required for spermatogenesis, a key reason providers and patients prefer it over TRT when preserving sperm production matters. For more on this, see our guide on enclomiphene's effect on fertility and sperm parameters.
Talk to a licensed provider
For anyone exploring an enclomiphene cycle, Book Your Consultation to connect with a licensed provider who will review your bloodwork and determine whether cycling enclomiphene is appropriate for your situation.
FAQ
Does enclomiphene need to be cycled?
Enclomiphene does not require cycling for everyone. Some men use it continuously under provider supervision while others complete defined courses with breaks. The structure depends on the diagnosis, treatment goals, and axis response, all determined from bloodwork by the provider.
How long should an enclomiphene cycle last?
Most published protocols range from several weeks to a few months, and trial durations varied across the RCTs analyzed by Hohl et al. in 2025. A licensed provider sets the cycle length based on baseline labs, the therapeutic goal, and how the hormone axis responds to treatment.
Can you take enclomiphene on a steroid cycle?
Using enclomiphene during active anabolic steroid use has limited practical effect on endogenous testosterone, because exogenous androgens suppress the axis regardless of estrogen-receptor blockade. Its more recognized use is as post-cycle therapy, after steroids have cleared, to restart gonadotropin signaling and testicular function.
What happens when you stop taking enclomiphene?
The hypothalamic estrogen-receptor blockade ends, and the negative feedback loop gradually resumes. For men who used enclomiphene for secondary hypogonadism, testosterone levels typically return toward the pre-treatment baseline over weeks because the underlying cause of low testosterone has not been resolved. Men who also addressed contributing lifestyle factors during treatment may see a more sustained response.
Is enclomiphene safe for long-term use?
Clinical data from multiple RCTs analyzed in the 2025 meta-analysis by Hohl et al. found acceptable tolerability over the trial durations reviewed, with hot flashes, mood changes, and headaches as the most noted side effects. Long-term data beyond those trial periods is still accumulating, and providers monitor labs regularly throughout any extended enclomiphene cycle.
Sources
- Rodriguez KM et al. (2016). Enclomiphene citrate for the treatment of secondary male hypogonadism. Expert Opinion on Pharmacotherapy. PubMed
- Hohl A et al. (2025). Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Archives of Endocrinology and Metabolism. PubMed
You May Also Like
 Enclomiphene
 Before and After: Physical Changes Explained
Enclomiphene before and after: what physical changes to expect, how the results timeline unfolds, and why provider monitoring matters for outcomes.
October 21, 2026 ETRead more → Enclomiphene
 Vision Side Effects: Eye Floaters & More
Enclomiphene vision side effects include eye floaters, blurry vision, and light sensitivity. Know the warning signs and when to contact your provider.
October 21, 2026 ETRead more → Enclomiphene
 Drug Test: Detection, WADA, and Disclosure
Enclomiphene drug test detection depends on the test type. Learn how workplace panels, military screening, and WADA rules treat this SERM.
October 21, 2026 ETRead more →