
The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Enclomiphene testicle size effects differ fundamentally from those of testosterone replacement therapy. Where TRT suppresses the gonadotropin signals that keep testes active, enclomiphene drives the pituitary to release more LH and FSH, maintaining the hormonal input testes need to function. The distinction matters clinically. Men exploring their options for treating secondary hypogonadism will find that enclomiphene keeps the HPG axis intact rather than bypassing it. Clinical studies show inconsistent results on whether the drug enlarges testicles above a normal baseline, but consistent evidence that it does not cause the atrophy associated with exogenous testosterone.
How enclomiphene acts on testicular function

Enclomiphene is the trans-isomer of clomiphene citrate, isolated from the cis-isomer zuclomiphene. It functions as a selective estrogen receptor modulator (SERM). By blocking estrogen receptors at the hypothalamus and pituitary, enclomiphene prompts the brain to read low estrogen and respond with increased GnRH release. That cascade raises both LH and FSH.
LH activates Leydig cells inside the testes. Leydig cells respond by synthesizing testosterone. FSH, working in parallel, activates Sertoli cells within the seminiferous tubules, the structural cells that support sperm maturation at each stage of development. Both cell types must stay active for the testes to maintain volume and function.
This upstream mechanism forms the cellular basis of enclomiphene testicle size preservation. Ongoing gonadotropin drive keeps Leydig and Sertoli cells active rather than allowing them to go dormant. A 2016 review in Expert Opinion on Pharmacotherapy confirmed that enclomiphene raised LH, FSH, and testosterone in men with secondary hypogonadism while preserving the hormonal environment that supports testicular health [Rodriguez et al., 2016].
Preclinical animal studies add histological detail to this picture. Researchers measured testicular weight across dose levels and found that increased gonadotropin output correlated with Leydig cell proliferation, changes in seminiferous tubule diameter, and increases in overall testicular weight. These structural markers suggest genuine trophic effects on testicular tissue, consistent with what the hormonal data predicts.
Enclomiphene vs TRT testicles: a side-by-side comparison
| Factor | Enclomiphene | TRT (exogenous testosterone) |
|---|---|---|
| LH and FSH output | Elevated | Suppressed |
| Leydig cell activity | Maintained or increased | Reduced over time |
| Testicular volume | Maintained or modestly increased | Often reduced over time |
| Spermatogenesis | Preserved or improved | Significantly impaired |
| Fertility impact | Neutral to positive | Negative |
| HPG axis status | Intact and active | Bypassed |
This contrast helps explain why clinicians treating younger men with secondary hypogonadism often evaluate enclomiphene first when testicular health and fertility are clinical priorities. The pharmacological difference is not subtle.
Does enclomiphene make your testicles bigger?

Enclomiphene may modestly increase testicular volume in men with secondary hypogonadism, but consistent or dramatic enlargement above a normal baseline is not a reliable outcome across studies. Preservation is the more consistently documented effect.
By keeping LH and FSH elevated throughout treatment, enclomiphene ensures Leydig cells remain active and seminiferous tubules stay engaged with FSH-driven Sertoli cell support. For men who have experienced reduced testicular volume due to low gonadotropin output, restoring that signal may allow partial structural recovery over several months. The degree of enclomiphene testicular volume recovery depends on the depth of prior gonadotropin deficiency and how long it persisted.
What the research shows on enclomiphene testicle size
A 2025 systematic review and meta-analysis in the Archives of Endocrinology and Metabolism analyzed randomized controlled trials comparing clomiphene and enclomiphene with controls in men with hypogonadism. It found significant improvements in LH, FSH, and testosterone with enclomiphene treatment [Hohl et al., 2025]. Individual trial results on testicular volume were mixed: some studies reported modest increases while others showed no significant difference from placebo.
That variability across studies likely reflects differences in patient selection. Men starting with clearly reduced testicular volume had more room for measurable change. Men near a normal baseline generally showed maintenance rather than growth. Both are meaningful enclomiphene testicle size outcomes depending on the clinical context.
Preclinical animal models provide supporting cellular detail. Studies measuring testicular weight at multiple dose levels found dose-responsive increases in testicular mass, with histological analysis confirming Leydig cell proliferation and structural changes in seminiferous tubule architecture as gonadotropin-driven effects scaled up. The dose-response relationship is consistent with gonadotropin stimulation as the primary driver of testicular structural maintenance.
A licensed provider assesses baseline hormone levels and testicular function before recommending any course of therapy. The appropriate path depends on individual labs and clinical presentation.
How long does enclomiphene take to affect testicle size?
Enclomiphene testicle size changes follow a slower timeline than biochemical hormone changes. This reflects a fundamental biological constraint, not a limitation of the therapy.
LH and FSH begin rising within the first weeks as the pituitary responds to estrogen receptor blockade. Serum testosterone typically follows within the first month when the therapy is working as expected. These early hormonal shifts are what providers track to confirm biochemical response.
Structural changes in testicular tissue operate on a different clock. Spermatogenesis runs a roughly 74-day cycle in humans from initiation to completion. Any measurable change in sperm parameters, or in tubular volume reflecting spermatogenic activity, lags the hormonal shift by at least two to three months. That lag is not negotiable. Physical exam or ultrasound measurements of testicular volume typically show meaningful change, when they occur, after three to six months of consistent treatment.
Men recovering from TRT-induced testicular suppression often need longer. Duration of prior suppression, degree of atrophy at baseline, and individual HPG axis responsiveness all shape the recovery timeline. No universal number applies across patients.
The degree of potential volume recovery also depends on the underlying cause. Men whose testicular atrophy was primarily driven by gonadotropin deficiency have a better functional prognosis than men with primary testicular damage that was not hormonally driven. Lab work and physical assessment help a provider distinguish between these scenarios and set realistic expectations.
Practically: hormone panels in the early weeks establish whether enclomiphene is generating the right biochemical signal. Structural markers tell a different story that only becomes visible over months. A provider outlines monitoring intervals matched to your clinical situation.
Does enclomiphene prevent testicular atrophy from TRT?
Yes. Preventing testicular atrophy is one of the clearest clinical arguments for enclomiphene over TRT when testicular function and fertility matter to the patient.
Testicular atrophy from TRT follows a predictable pharmacological pathway. When testosterone enters from an external source, the pituitary detects adequate circulating levels and reduces GnRH, LH, and FSH. Leydig cells receive no activation signal. Sertoli cells lose FSH drive. The testes shrink. This is not a rare adverse event. It is a consistent consequence of long-term exogenous testosterone.
Enclomiphene does the opposite. It raises LH and FSH, keeping Leydig cells active and Sertoli cells engaged. The testes stay stimulated. The question of whether enclomiphene shrinks testicles has a clear mechanistic answer: it cannot cause atrophy through the same pathway because it never suppresses gonadotropin output. Enclomiphene testicular atrophy prevention is built directly into how the drug works, not incidental to it.
Kharaba et al. (2020) documented the suppressive effect of exogenous testosterone on endogenous LH, FSH, and testosterone production in their review of TRT's adverse impacts, identifying gonadotropin suppression as a consistent pharmacological consequence of testosterone therapy [Kharaba et al., 2020]. This suppression is the primary driver of TRT-related testicular atrophy.
For men currently on TRT who notice testicular atrophy, transitioning to enclomiphene is an option some providers discuss when labs support it. Assessment typically includes hormone panels to confirm the degree of gonadotropin suppression and evaluate current testicular function. A licensed provider determines whether a therapy is appropriate after reviewing your intake. Enclomiphene testicle size preservation is most likely when the atrophy is primarily hormonal in origin rather than structural.
For a broader clinical overview of how the two approaches differ, see how enclomiphene citrate compares to other testosterone treatments.
Can enclomiphene cause testicular pain?
Testicular discomfort is uncommon but documented as a reaction to enclomiphene therapy. It arises from the hormonal shift the drug induces rather than from direct tissue damage.
When enclomiphene blocks estrogen receptors at the hypothalamus and pituitary, LH and FSH rise sharply. The testes respond to this sudden increase in gonadotropin stimulation by ramping up activity: Leydig cells accelerate testosterone synthesis, Sertoli cells receive stronger FSH activation, and spermatogenic activity picks up. This rapid functional increase can produce a sensation of pressure or mild aching in the testes, particularly in the early weeks when the hormonal shift is most pronounced.
The discomfort is typically transient. It tends to emerge during the initial period and fades as the body adapts to its new hormonal baseline. Most men who experience it describe it as mild and short-lived.
Persistent or severe testicular pain needs clinical evaluation. It could reflect the drug's hormonal mechanism, or it could indicate an unrelated condition that surfaced during treatment. A provider should assess severity, consider other possible causes, and adjust the plan if warranted. Pain should not be attributed to enclomiphene alone without a proper assessment.
For a full picture of the reactions associated with enclomiphene, enclomiphene's documented side effects and safety profile covers the range reported in clinical practice.
Enclomiphene, testosterone, and fertility
Enclomiphene testosterone fertility effects are mechanistically direct. Testosterone production and sperm production both depend on the same upstream gonadotropin signals, which is exactly what enclomiphene restores.
LH drives Leydig cells to produce testosterone. But the concentration required for spermatogenesis inside the testes, called intratesticular testosterone, runs far higher than circulating serum levels reflect. This gradient cannot be replicated by delivering testosterone from outside the body. Serum levels rise with exogenous testosterone, but intratesticular testosterone falls because Leydig cells are no longer being activated. The mechanism that creates the gradient spermatogenesis depends on is bypassed entirely.
FSH activates Sertoli cells simultaneously, which provide the structural and nutritional environment for sperm maturation through each stage of development within the seminiferous tubules. Raise both LH and FSH and you support both processes at once. TRT suppresses both signals. Sperm counts can fall significantly within months of starting exogenous testosterone, even when serum testosterone looks adequate.
Clomiphene testicular function research established the foundational principle before enclomiphene was isolated as a pure compound. SERM-based stimulation of the HPG axis can restore fertility markers in men with hypogonadotropic hypogonadism without the reproductive consequences of exogenous hormone. Enclomiphene refines this approach by removing zuclomiphene, the cis-isomer that accumulates in tissue, carries a much longer half-life, and contributes estrogenic rather than antiestrogenic activity at the receptor level.
A 2016 review in Expert Opinion on Pharmacotherapy described enclomiphene as an option specifically suited to men with secondary hypogonadism who need testosterone restoration while maintaining reproductive capacity [Rodriguez et al., 2016]. The enclomiphene testicle size benefits and the fertility benefits share the same origin: an intact, gonadotropin-driven HPG axis.
Men who want to establish a hormone baseline before their first provider consultation can use at-home hormone testing to check testosterone and relevant markers in advance.
What do before and after results look like for enclomiphene and testicle size?
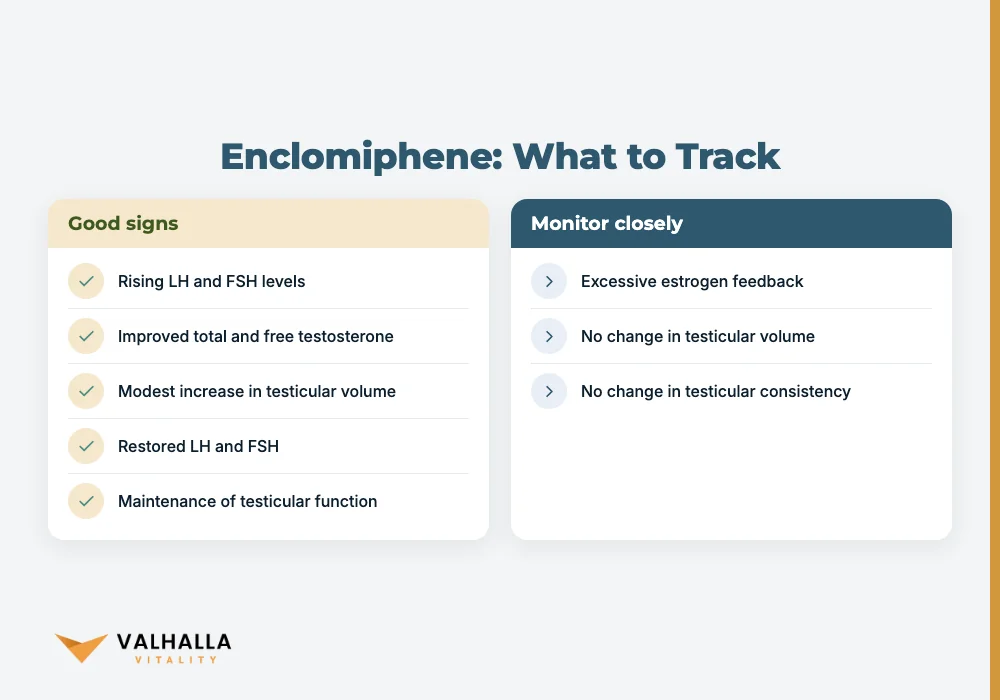
Clinical trials and provider monitoring evaluate enclomiphene testicle size through specific, measurable parameters rather than subjective assessment. These are the markers tracked in research protocols and clinical follow-up:
Hormone markers (assessed in the first 4 to 8 weeks):
- LH and FSH: rising levels confirm the pituitary is responding to estrogen receptor blockade
- Total and free testosterone: reflect Leydig cell output
- Estradiol: monitored to ensure aromatization does not produce excessive estrogen feedback
Structural markers (assessed at 3 to 6 months when relevant):
- Testicular volume: measured by physical exam or ultrasound; normal adult range is roughly 15 to 25 mL per testis
- Testicular consistency: changes in firmness may indicate functional shifts in tissue structure
Fertility markers (when reproductive goals are a clinical priority):
- Sperm count, motility, and morphology from semen analysis
- Inhibin B: a Sertoli-cell-specific marker that directly reflects active spermatogenesis
In men with secondary hypogonadism starting from a low gonadotropin baseline, the trajectory documented over three to six months typically includes restored LH and FSH, improved testosterone, and, in some cases, modest increases in testicular volume. The 2025 meta-analysis by Hohl et al. confirmed significant gonadotropin improvements in enclomiphene RCTs, with testicular volume responses varying between individual trials [Hohl et al., 2025].
Men with near-normal baseline testicular function typically show maintenance rather than growth. Both outcomes are clinically meaningful depending on the starting point. A licensed provider determines the appropriate monitoring schedule and defines what constitutes a meaningful response for each individual.
Tracking enclomiphene testicle size during treatment
Regular monitoring confirms that therapy is producing the intended hormonal response and allows early identification of unexpected changes in testicular health.
Hormone panels form the foundation. LH, FSH, total testosterone, and estradiol are assessed at intervals a provider sets based on treatment phase and initial response. Rising gonadotropins confirm pituitary activation. Testosterone rising in parallel confirms Leydig cell response. Estradiol is tracked because elevated estrogen can create a feedback signal that partially limits the gonadotropin response even when the drug is otherwise working.
Physical assessment of testicular volume, by exam or ultrasound, may be included for men who had reduced volume at baseline or are transitioning from TRT. Normal adult testicular volume runs roughly 15 to 25 mL per testis. A provider uses baseline measurements as the reference point against which to evaluate enclomiphene testicle size changes over the course of treatment.
Semen analysis is relevant when fertility is a clinical goal. It provides a direct functional read on Sertoli cell activity and spermatogenic health that hormone panels alone cannot fully capture. Sperm parameters typically take three to six months to reflect hormonal improvements from enclomiphene therapy, given the length of the spermatogenic cycle.
Any unexpected decline in testicular volume during treatment, rather than maintenance or improvement, prompts reassessment. The cause could be insufficient gonadotropin response, excessive estrogen feedback, or an unrelated testicular issue. Early detection allows for timely adjustments to the treatment plan. Availability varies by state. At Valhalla Vitality, a licensed provider outlines the monitoring cadence appropriate for your clinical situation.
Ready to discuss enclomiphene with a licensed provider?
If you have questions about enclomiphene testicle size effects or want to understand whether enclomiphene is appropriate for your situation, Book Your Consultation to connect with a licensed provider who reviews your intake and labs before making any recommendations.
FAQ
Does enclomiphene shrink testicles?
Enclomiphene does not cause testicular atrophy. It raises LH and FSH, keeping the testes actively stimulated throughout treatment. The mechanism is the opposite of TRT, which suppresses gonadotropins and is the therapy most commonly associated with testicular shrinkage.
How does enclomiphene compare to TRT for testicular health?
TRT suppresses LH and FSH, reducing Leydig cell activity and leading to testicular atrophy over time. Enclomiphene raises both gonadotropins and maintains continuous testicular stimulation. For men who want to preserve testicular volume and fertility potential, the two approaches produce meaningfully different outcomes.
Is enclomiphene the same as clomiphene?
No. Enclomiphene is the trans-isomer of clomiphene citrate, separated from zuclomiphene, the cis-isomer. Zuclomiphene accumulates in tissue, has a much longer half-life, and has estrogenic rather than antiestrogenic activity at the receptor, which gives enclomiphene a cleaner hormonal profile.
Can enclomiphene support fertility?
Enclomiphene raises both LH and FSH simultaneously, supporting testosterone production and spermatogenesis at the same time. This dual gonadotropin effect makes it a consideration for men with secondary hypogonadism who want to address hormone levels without compromising fertility potential.
How is testicular health monitored during enclomiphene treatment?
A licensed provider determines the monitoring schedule based on clinical presentation, baseline labs, and treatment goals. Hormone panels are assessed most frequently in early treatment; testicular volume and semen analysis are added when clinically relevant. Availability varies by state.
Sources
- Hohl A et al. (2025). Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Archives of Endocrinology and Metabolism. PubMed
- Rodriguez KM et al. (2016). Enclomiphene citrate for the treatment of secondary male hypogonadism. Expert Opinion on Pharmacotherapy. PubMed
- Kharaba ZJ et al. (2020). Effectiveness of testosterone therapy in hypogonadal patients and its controversial adverse impact on the cardiovascular system. Critical Reviews in Toxicology. PubMed
You May Also Like
 Enclomiphene
 Blood Pressure: What Men Need to Know
Enclomiphene blood pressure effects explained: does this therapy raise or lower BP, what to monitor, and how cardiovascular health fits the picture.
October 9, 2026 ETRead more → Enclomiphene
Best Time to Take Enclomiphene: Morning or Evening?
Best time to take enclomiphene, morning or night, depends on side effects and routine. Providers set enclomiphene citrate timing after reviewing labs.
October 9, 2026 ETRead more → Enclomiphene
 Peptide: What Men Need to Know About This SERM
Enclomiphene peptide is a SERM that supports natural testosterone. Learn how it works, how it differs from clomiphene, and whether you may qualify.
October 9, 2026 ETRead more →