
The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Enclomiphene mechanism of action targets estrogen receptors in the hypothalamus and pituitary gland. Blocking those receptors removes the feedback signal that suppresses LH and FSH, so the pituitary releases more of both hormones and the testes produce more testosterone. The mechanism works within the body's own hormonal system. For men considering enclomiphene therapy for low testosterone, this distinction matters.
What is enclomiphene?
Enclomiphene is the trans-isomer of clomiphene citrate. That single phrase contains the key to how enclomiphene works differently from the compound it was derived from.
Clomiphene citrate has been used in reproductive medicine for decades. It is a mixture of two structurally distinct molecules called isomers: the trans form, which is enclomiphene, and the cis form, called zuclomiphene.
Both bind estrogen receptors, but they do not behave the same way. Enclomiphene is a pure anti-estrogen: it occupies the receptor without activating it. Zuclomiphene retains partial estrogenic activity. It also clears from the body far more slowly, meaning it accumulates with repeated dosing and exerts a mixed estrogenic and anti-estrogenic signal long after the drug is stopped.
Separating enclomiphene from the mixture was a deliberate step toward a pharmacologically cleaner compound. Without zuclomiphene, the remaining molecule blocks estrogen receptors without partially activating them. That chemical purity is central to why enclomiphene mechanism of action produces a more defined hormonal response than clomiphene does in clinical settings.
Enclomiphene belongs to the selective estrogen receptor modulator (SERM) class, sharing the enclomiphene SERM designation with compounds such as tamoxifen and raloxifene. All three bind estrogen receptors but produce tissue-specific effects depending on which receptor subtype is expressed and which molecular co-regulators are present. What makes enclomiphene specifically relevant to men's hormone health is its antagonist behavior at the hypothalamic estrogen receptors that govern testosterone output.
How is enclomiphene different from clomiphene?
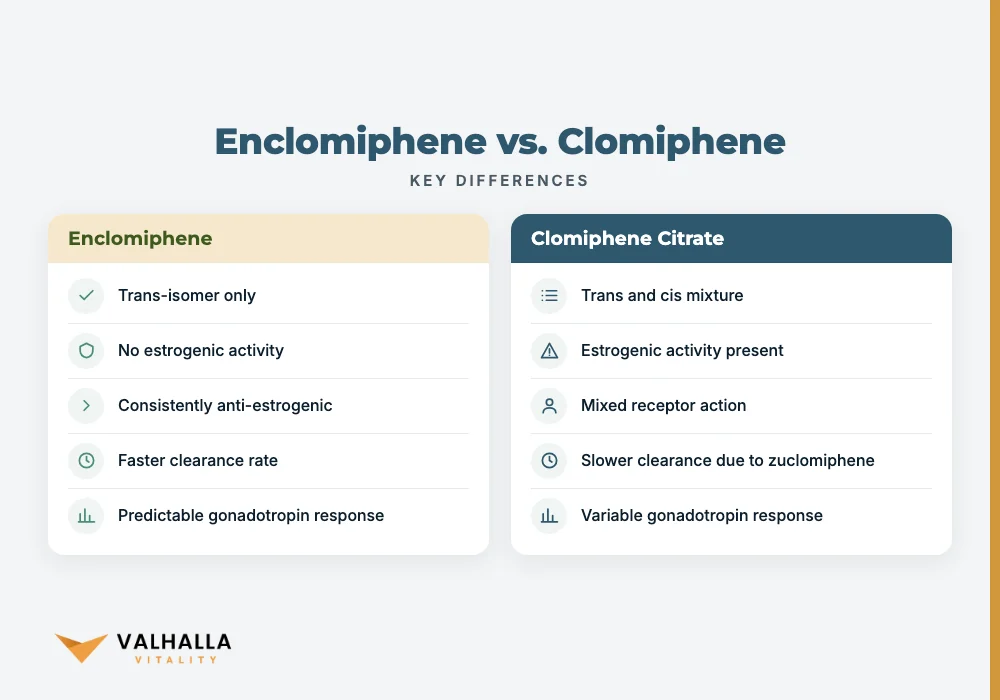
Enclomiphene vs clomiphene comes down to what happens when zuclomiphene is removed from the equation.
| Feature | Enclomiphene | Clomiphene citrate |
|---|---|---|
| Isomer composition | Trans-isomer only | Trans + cis mixture |
| Estrogenic activity | None | Present via zuclomiphene |
| Receptor action at HPG axis | Consistently anti-estrogenic | Mixed: anti-estrogen and partial agonist |
| Clearance rate | Faster | Slower due to zuclomiphene accumulation |
| Gonadotropin response | Predictable | Variable |
The practical consequence is significant. When a drug sends mixed signals to the hypothalamic estrogen receptor, part of that signal works against the intended therapeutic effect. Zuclomiphene's partial agonism at the receptor partially reinforces the feedback suppression that enclomiphene is trying to remove.
Enclomiphene removes that ambiguity. Its signal at the receptor is consistently inhibitory. The hypothalamus reads the blocked receptor as absent estrogen and responds by ramping up GnRH pulsatility, which drives more LH and FSH release and supports greater testosterone production.
A 2025 systematic review and meta-analysis published in Archives of Endocrinology and Metabolism examined randomized controlled trials of enclomiphene for male hypogonadism and found consistent, measurable improvements in LH, FSH, and testosterone levels. The predictability the researchers observed aligns directly with enclomiphene's cleaner receptor pharmacology.
For men whose providers are weighing treatment options, this pharmacological difference is a key reason enclomiphene has attracted focused clinical attention as a standalone compound rather than as part of the original clomiphene mixture.
How does enclomiphene work in the body?
Enclomiphene does not deliver hormones. It does not add testosterone. It changes the signaling environment at the top of the hormonal chain so the body's own production machinery receives a stronger cue. That is the core of how enclomiphene works.
The HPG axis: the control system for testosterone
The hypothalamic-pituitary-gonadal (HPG) axis is the hormonal communication network that governs testosterone production in men. It begins at the hypothalamus, a brain region that releases gonadotropin-releasing hormone (GnRH) in timed pulses. These pulses are not uniform. Their frequency and amplitude carry an instruction that the pituitary gland reads carefully.
The pituitary responds by releasing luteinizing hormone (LH) and follicle-stimulating hormone (FSH). LH travels through the bloodstream to the testes, where it binds receptors on Leydig cells. Leydig cells convert cholesterol to testosterone in response. FSH targets Sertoli cells, supporting their role in sperm maturation.
The axis regulates itself through negative feedback. Testosterone and estradiol produced by the testes travel back to the hypothalamus and pituitary. When those levels are sufficient, they activate inhibitory pathways that reduce GnRH pulsatility and lower gonadotropin secretion. The brain backs off. When levels fall, the feedback signal weakens, GnRH pulses increase, and the chain ramps back up.
Secondary hypogonadism is a disruption of this loop at the signaling level. The testes are not damaged. They can produce testosterone when properly stimulated.
The problem is that the upstream signal is too weak or suppressed, leaving Leydig cells understimulated. That is precisely where enclomiphene mechanism of action applies: at the estrogen receptor in the hypothalamus, where the feedback suppression is occurring.
Enclomiphene LH FSH: the hormonal cascade
Enclomiphene occupies estrogen receptors in the hypothalamus. With those receptors blocked, estradiol cannot deliver its inhibitory signal. The hypothalamus interprets this as a deficiency state and increases GnRH pulse frequency.
The pituitary responds. LH output rises. So does FSH.
Both hormones travel to the testes in higher concentrations than before treatment. Elevated LH drives Leydig cell activation and accelerates testosterone synthesis. Elevated FSH supports Sertoli cell function and the developmental process of spermatogenesis.
This enclomiphene LH FSH response has a clinically important implication: it preserves testicular function. Exogenous testosterone replacement raises circulating testosterone from an outside source, but it suppresses LH and FSH through negative feedback. The testes stop receiving stimulation.
Enclomiphene does the opposite. It keeps LH and FSH elevated, the testes remain stimulated, and the downstream effects on fertility may be preserved. Providers monitoring enclomiphene treatment measure LH, FSH, testosterone, and estradiol at regular intervals to confirm the cascade is responding as expected.
Is enclomiphene a SERM?
Yes. Enclomiphene is a selective estrogen receptor modulator. That classification is more specific than it first appears.
A SERM is not simply an estrogen blocker. Blocking estrogen across all tissues would disrupt bone density, lipid metabolism, cardiovascular function, and libido, all of which depend on estrogen signaling to varying degrees in men. A non-selective estrogen antagonist would create as many problems as it solved.
What makes enclomiphene a SERM is that its receptor effects depend on which estrogen receptor subtype is expressed in a given tissue and which molecular co-regulators are present.
In the hypothalamus and pituitary, where ER-alpha mediates the inhibitory feedback on testosterone production, enclomiphene acts as an antagonist. In other tissues where ER-beta predominates or where co-regulator expression differs, the compound's behavior produces different, often less pronounced effects.
Enclomiphene as a SERM is clinically practical because its site-selective antagonism at the HPG axis removes feedback suppression on testosterone without globally suppressing estrogen in every tissue. Bone turnover, cardiac function, and estrogen-dependent neurological processes continue to receive estrogen signaling. The HPG axis is the specific target.
Other SERMs in clinical use illustrate how broadly this pharmacological approach can be applied. Tamoxifen targets ER-alpha in breast tissue. Raloxifene addresses ER-alpha in bone while sparing uterine tissue. Enclomiphene's niche is defined by its activity at hypothalamic-pituitary receptor sites that govern testosterone output in men.
For a more complete picture of how enclomiphene fits into clinical hormone health protocols, the SERM mechanism is one part of the story.
What receptors does enclomiphene bind to?
Enclomiphene binds to both major subtypes of the nuclear estrogen receptor: estrogen receptor alpha (ER-alpha) and estrogen receptor beta (ER-beta).
Both subtypes belong to the nuclear receptor superfamily. Their tissue distribution differs substantially. ER-alpha is densely expressed in the hypothalamus, pituitary gland, liver, and breast tissue. ER-beta appears more broadly across the testes, ovaries, colon, lung, and bone.
In the hypothalamus and pituitary, ER-alpha mediates estrogen's inhibitory feedback on testosterone production. When estradiol binds ER-alpha in those regions, it activates suppressive gene expression programs that reduce GnRH pulsatility and lower LH and FSH secretion. Enclomiphene competes for the same binding site. It occupies the receptor without triggering the suppressive program.
This is what enclomiphene estrogen receptors blockade means in clinical terms. Not a general shutdown of estrogen signaling across all tissues, but a targeted occupation of ER-alpha at the anatomical sites where that receptor drives negative feedback on testosterone production.
ER-beta engagement by enclomiphene produces different downstream consequences because ER-beta activates different target genes and is present in tissues where the outcomes of receptor blockade differ. The clinical significance of enclomiphene's ER-beta activity at non-HPG sites remains an area of ongoing investigation.
The tissue selectivity underlying enclomiphene mechanism of action is what separates it from a blunt estrogen antagonist. The binding is targeted. The effect on the HPG axis is predictable. The effects elsewhere are tissue-dependent rather than uniform.
How does enclomiphene increase testosterone naturally?
Enclomiphene increases testosterone by removing a brake rather than pressing an accelerator. The testes in men with secondary hypogonadism contain functional Leydig cells. Those cells can produce testosterone. What they lack is adequate stimulation.
Here is the sequence of events:
- Enclomiphene binds estrogen receptors in the hypothalamus and pituitary
- Estradiol cannot deliver its inhibitory feedback signal
- GnRH pulse amplitude and frequency increase
- The pituitary secretes more LH and FSH into circulation
- LH reaches the testes and activates Leydig cell testosterone synthesis
- FSH supports Sertoli cell function and sperm development
- Circulating testosterone rises as the testes respond to the stronger upstream signal
What distinguishes enclomiphene testosterone production from exogenous supplementation is that the HPG axis remains active throughout. The body produces more testosterone rather than receiving it from an outside source. LH and FSH remain elevated. The testes stay stimulated.
The systematic review by Hohl et al. (2025), analyzing randomized controlled trials of enclomiphene for male hypogonadism, found that this gonadotropin-mediated testosterone-raising effect was consistent across the trials reviewed.
A licensed provider determines whether this pathway is appropriate for a given patient after reviewing symptoms, lab values, and medical history. The hormonal response varies between individuals, and not every case of low testosterone involves the kind of secondary, signaling-level deficit that enclomiphene addresses.
Secondary hypogonadism: the clinical context for enclomiphene

Enclomiphene mechanism of action applies specifically to secondary hypogonadism, and that specificity matters clinically.
| Secondary hypogonadism | Primary hypogonadism | |
|---|---|---|
| Problem location | Hypothalamus or pituitary | Testes themselves |
| LH and FSH levels | Low or inappropriately normal | Elevated |
| Testicular capacity | Intact | Impaired or absent |
| Enclomiphene relevant? | Yes | No |
Secondary hypogonadism means the testes retain functional capacity but are not receiving adequate upstream stimulation. The hypothalamus generates too little GnRH, the pituitary underresponds, or elevated estradiol excessively suppresses the feedback loop. In each case, the testes can produce testosterone if properly driven.
Primary hypogonadism is a different category. The testes are damaged, absent, or incapable of responding to stimulation. No upstream signal change can compensate for non-functional Leydig cells. Enclomiphene has no role in primary hypogonadism because the problem is not in the feedback loop but in the target organ.
Distinguishing between the two requires lab work. Total testosterone alone is insufficient. In secondary hypogonadism, LH and FSH are typically low or inappropriately normal relative to a low testosterone reading. In primary hypogonadism, LH and FSH are elevated as the brain attempts to drive the underperforming testes. A licensed provider makes this determination through morning testosterone measurements, repeat testing, concurrent gonadotropin levels, and clinical evaluation.
Factors that commonly contribute to secondary hypogonadism include age-related decline in GnRH pulsatility, elevated body adiposity, chronic sleep disruption, and certain medications. Adipose tissue expresses aromatase, the enzyme that converts testosterone to estradiol. Higher body fat therefore raises circulating estradiol, adding to feedback suppression of the HPG axis. This creates a self-reinforcing pattern that can further lower testosterone over time, making upstream intervention at the receptor level a clinically rational approach.
Safety, monitoring, and the provider's role
Understanding enclomiphene mechanism of action is one part of the clinical picture. Monitoring the treatment response is the other.
Because enclomiphene modulates the estrogen receptor pathway, both testosterone and estradiol typically rise during effective treatment. More testosterone in circulation increases the substrate available for aromatase, which converts testosterone to estradiol. If estradiol rises disproportionately, it can partially counteract the benefits and introduce unwanted effects, including mood changes and fluid retention. Monitoring estradiol is therefore a standard part of enclomiphene therapy, not an afterthought.
Lab panels typically include:
- Total testosterone and free testosterone
- Luteinizing hormone (LH)
- Follicle-stimulating hormone (FSH)
- Estradiol
- Hematocrit
These values tell the provider whether the gonadotropin response is appropriate, whether testosterone is tracking upward as expected, whether estradiol is within an acceptable range, and whether red blood cell production is being affected. For a complete review of adverse effects and safety monitoring during enclomiphene therapy, the clinical detail is worth reading before starting treatment.
A licensed provider determines the approach after reviewing the patient's full intake and baseline labs. No universal protocol applies because the hormonal response varies with age, baseline hormone levels, body composition, and the underlying reason the HPG axis is suppressed.
For men in the US, Valhalla Vitality offers a structured telehealth pathway: online medical intake, provider review within 24 business hours, and prescription fulfillment through a partner US compounding pharmacy approximately 3 to 7 business days after the prescription is transmitted. Availability varies by state.
Ready to explore enclomiphene therapy?
If the mechanism described here raises questions about whether enclomiphene may be relevant to your hormone health, Book Your Consultation with a licensed provider who can review your intake and labs.
FAQ
What is the enclomiphene mechanism of action?
Enclomiphene blocks estrogen receptors in the hypothalamus and pituitary, removing the inhibitory feedback that suppresses LH and FSH. The pituitary responds by releasing more of both hormones, and the testes increase testosterone output as a result. The entire process works within the body's own hormonal signaling axis.
Is enclomiphene a SERM?
Yes. Enclomiphene is a selective estrogen receptor modulator that acts as an antagonist at hypothalamic and pituitary estrogen receptors while producing tissue-dependent effects elsewhere. This selectivity allows it to raise LH, FSH, and testosterone without globally suppressing estrogen across all tissues.
How does enclomiphene differ from testosterone replacement therapy?
Enclomiphene stimulates the body's own testosterone production by acting on the HPG axis, while testosterone replacement delivers testosterone from an external source. Because enclomiphene preserves LH and FSH signaling to the testes, it may also support sperm production, which exogenous testosterone typically suppresses.
Does enclomiphene affect sperm production?
Enclomiphene raises FSH alongside LH. Since FSH drives spermatogenesis, rising FSH levels may support sperm production. This distinguishes enclomiphene from testosterone replacement therapy, which suppresses FSH and can reduce fertility. A licensed provider evaluates whether this distinction is clinically relevant for each individual.
Who is a candidate for enclomiphene?
Enclomiphene is studied in men with secondary hypogonadism, where the testes are functional but the upstream hormonal signal is insufficient. A licensed provider determines candidacy after reviewing lab values, symptoms, and medical history. Availability varies by state.
Sources
- Hohl A et al. (2025). Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Archives of endocrinology and metabolism. PubMed
You May Also Like
 Enclomiphene
 Before and After: Physical Changes Explained
Enclomiphene before and after: what physical changes to expect, how the results timeline unfolds, and why provider monitoring matters for outcomes.
October 21, 2026 ETRead more → Enclomiphene
 Vision Side Effects: Eye Floaters & More
Enclomiphene vision side effects include eye floaters, blurry vision, and light sensitivity. Know the warning signs and when to contact your provider.
October 21, 2026 ETRead more → Enclomiphene
 Drug Test: Detection, WADA, and Disclosure
Enclomiphene drug test detection depends on the test type. Learn how workplace panels, military screening, and WADA rules treat this SERM.
October 21, 2026 ETRead more →