Testosterone Undecanoate vs Cypionate: Full TRT Guide

The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Testosterone undecanoate vs cypionate represent two distinct paths within injectable testosterone therapy: one ester requires more frequent injections and delivers faster early symptom relief, the other supports much longer gaps between doses, with an oral capsule form that requires no injections at all. Both can restore testosterone to a therapeutic range when prescribed correctly. A licensed provider determines which form fits your labs, health history, and daily routine after a thorough intake review.
Testosterone undecanoate vs cypionate: understanding the ester difference

Both testosterone cypionate and testosterone undecanoate deliver the same hormone. The difference is the ester chain bonded to the testosterone molecule. That chain controls how quickly the compound releases after injection, how high levels peak, and how long they stay active before the next dose is needed. Longer chains mean slower release, flatter peaks, and wider spacing between doses. Shorter chains do the opposite.
Testosterone cypionate uses a medium-length ester. It releases quickly after injection, peaks within one to two days, and clears within roughly two weeks. That clearance curve is why cypionate protocols require regular short-interval injections to maintain steady levels.
Testosterone undecanoate carries the longest ester in common clinical use. Injectable undecanoate releases very slowly from the intramuscular depot, producing a flat level profile over a much longer period. The oral capsule form works differently again. It absorbs through the intestinal lymphatic system rather than entering portal circulation directly, which changes how the liver processes it. A 2025 review in Sexual Medicine Reviews by Goldstein et al. examined newer oral testosterone undecanoate formulations specifically regarding this hepatic exposure question.
For anyone searching nebido vs cypionate or aveed vs cypionate: Nebido and Aveed are brand names for injectable testosterone undecanoate. Everything in this testosterone ester comparison applies to those formulations directly.
Key differences at a glance
| Feature | Testosterone cypionate | Injectable testosterone undecanoate | Oral testosterone undecanoate |
|---|---|---|---|
| Route | Intramuscular injection | Intramuscular injection | Capsule with food |
| Dosing interval | Shorter (provider-determined) | Much longer (provider-determined) | Multiple times daily (provider-determined) |
| Liver first-pass | Bypassed | Bypassed | Reduced via lymphatic absorption |
| Onset of symptom relief | Faster | Slower (loading phase takes weeks) | Gradual |
| Injection site reactions | Possible | Possible, larger injection volume | None |
| POME risk | Very low | Small but documented | Not applicable |
A licensed provider determines all dosing schedules and monitors labs throughout treatment.
Is testosterone undecanoate better than cypionate for TRT?
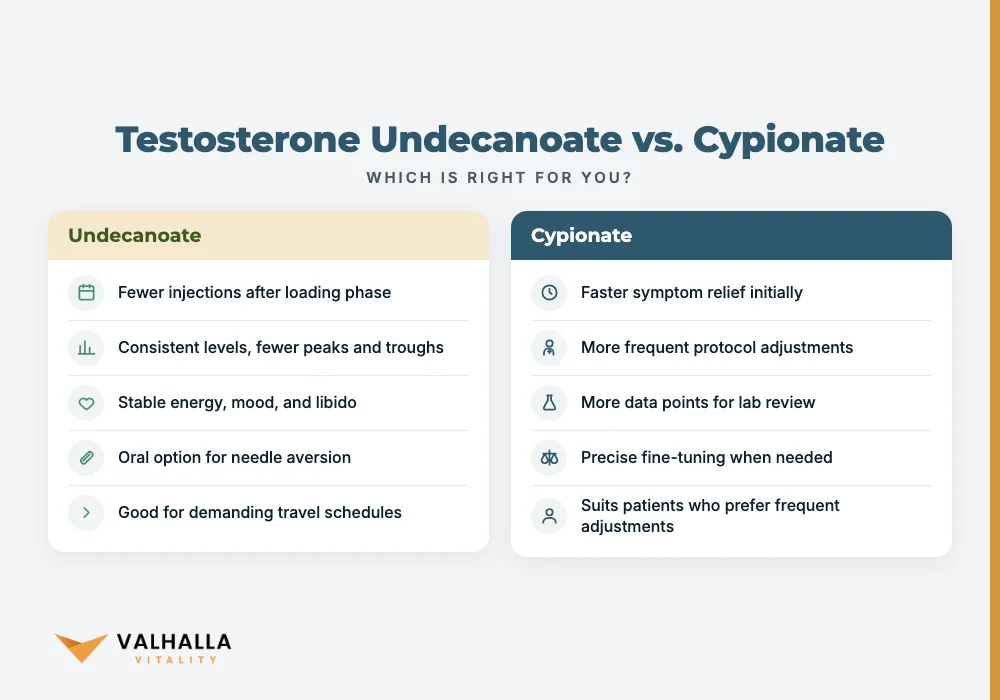
The short answer: it depends.
Injectable testosterone undecanoate requires far fewer injections once the loading phase is complete. A 2022 review in Endocrinology and Metabolism Clinics of North America by Wang et al. confirmed that long-acting testosterone undecanoate maintains therapeutic levels in hypogonadal men with fewer peaks and troughs than shorter-acting formulations. Fewer peaks and troughs tends to produce more consistent energy, mood, and libido between doses.
Testosterone cypionate suits patients who prefer more frequent opportunities to adjust the protocol. More injections mean more data points at each lab review. Providers can fine-tune more precisely when something changes. Cypionate also delivers symptom relief faster in the first weeks, which matters to patients who have been symptomatic for months or years.
Oral testosterone undecanoate changes the comparison entirely. No needles. For patients with needle aversion, demanding travel schedules, or limited access to injection supplies, oral TRT options like undecanoate capsules can be genuinely more practical. The tradeoff is real: multiple daily doses paired with fat-containing meals, strict adherence required. Miss a dose or take it without food and levels become unpredictable in ways that injectable therapy does not produce.
Patients searching sustanon vs cypionate: Sustanon is a blend of multiple testosterone esters, not a single ester. It has a different release profile from both cypionate and undecanoate, and it is less commonly prescribed in US telehealth TRT protocols.
The clinical data on testosterone undecanoate vs cypionate shows tradeoffs in each direction, neither form is universally superior. No form wins this comparison outright. Every tradeoff in the testosterone ester comparison is real. The form that makes clinical sense depends on your labs and the judgment of a licensed provider.
Oral TRT options: how undecanoate capsules work
Oral testosterone has a complicated history. Earlier oral formulations were 17-alpha-alkylated compounds that survived digestion but were hepatotoxic. Testosterone undecanoate capsules are not 17-alpha-alkylated. They are lipophilic compounds that absorb through the intestinal lymphatic vessels, bypassing most of the hepatic first-pass effect.
This is not complete liver protection. The Goldstein et al. (2025) review in Sexual Medicine Reviews focused specifically on hepatic side effects and found that some liver exposure still occurs with newer oral TU formulations. Liver enzyme monitoring is standard practice throughout treatment. Patients with pre-existing liver conditions are typically not candidates for oral testosterone undecanoate.
Two oral testosterone undecanoate products are available by prescription in the US. Both require a prescription from a licensed provider and regular follow-up lab testing. The fat-meal requirement is not optional. Without dietary fat, absorption drops and levels become unpredictable. Patients who cannot consistently pair doses with fat-containing meals may find injectable options more reliably stable.
For a detailed look at how oral undecanoate capsules fit into a full hormone therapy protocol, a separate guide covers patient selection criteria and the full pharmacology.
How often do you need to inject testosterone cypionate?
Testosterone cypionate is typically administered every one to two weeks. Some providers prefer dividing doses into more frequent shorter intervals to reduce level fluctuations between injections.
That schedule is workable for many patients. Not frictionless. Consistent clinic visits or home self-injections, proper cold storage of supplies, and not missing doses all require ongoing discipline. For patients with unpredictable schedules or significant injection anxiety, that friction compounds over months and affects adherence.
Adherence matters clinically. Inconsistent injection intervals produce inconsistent testosterone levels, which undermines the therapy. A 2022 systematic review and Bayesian network meta-analysis in The Journal of Urology by Nackeeran et al. found that intramuscular testosterone routes, particularly those producing high peaks, were associated with greater hematocrit elevation than other delivery methods. Elevated hematocrit raises cardiovascular risk. Providers monitor it routinely throughout injectable testosterone therapy and adjust protocols when levels trend high.
Injectable testosterone undecanoate reduces the injection burden significantly once established. Fewer injections reduce adherence friction. But the loading phase at the start of treatment takes longer to establish stable levels, and the large injection volume means administration typically happens in a clinical setting rather than at home.
What are the side effects of testosterone undecanoate?
Side effects differ meaningfully between the oral and injectable forms of undecanoate.
Oral testosterone undecanoate most commonly causes GI effects: nausea, stomach discomfort, and bloating, particularly in the first few weeks. These often ease with time, but in some patients they persist. Liver enzyme monitoring is part of the standard protocol because some hepatic exposure occurs despite the lymphatic absorption route. The Goldstein et al. (2025) review found that liver enzyme elevations are possible with newer oral TU formulations and that careful patient selection and monitoring reduce but do not fully address this concern. Patients with pre-existing liver disease are typically excluded from oral TU protocols.
Injectable testosterone undecanoate carries a small but documented risk of pulmonary oil microembolism, or POME. This reaction involves oil particles entering pulmonary circulation shortly after intramuscular injection. A 2023 literature review in the International Journal of Impotence Research by Adam et al. documented POME cases linked specifically to injectable testosterone undecanoate. The large injection volume required for the extended-release depot contributes to this risk. For this reason, injectable testosterone undecanoate is administered in a clinical setting with a post-injection observation period, typically at least 30 minutes.
Both forms share the general side effects of all testosterone therapy. Hematocrit elevation, acne, oily skin, and mood changes are all possible. And critically, all testosterone therapy suppresses natural sperm production. A 2025 review in Nature Reviews Urology by Naelitz et al. confirmed that TRT consistently suppresses spermatogenesis in reproductive-age men, regardless of which form is used. This is a significant consideration for men who want to preserve fertility.
Which testosterone form has fewer injection site reactions?
Oral testosterone undecanoate has none. It is a capsule. Zero injections involved.
Among injectable options, both testosterone cypionate and injectable testosterone undecanoate can cause local reactions at the injection site: soreness, redness, bruising, and swelling. For most patients these are mild and temporary. For some, they become a recurring inconvenience that affects willingness to continue treatment.
Injectable testosterone undecanoate requires a larger injection volume than cypionate. Larger volumes correlate with more pronounced local discomfort in some patients. This is a practical factor worth discussing with a provider when choosing between injectable forms.
If injection site reactions have been a persistent problem during testosterone therapy, that is a specific data point worth raising with a licensed provider. Switching to a different form or route may improve tolerability. A licensed provider determines whether a change is appropriate after reviewing your response history and labs.
Can you switch from injectable to oral testosterone?
Yes, but not by simply substituting one product for another. This is not a direct swap.
Testosterone undecanoate vs cypionate: key considerations for a supervised switch
Switching from testosterone cypionate to oral testosterone undecanoate requires a supervised transition and a new dose-finding period guided by labs. Cypionate injects directly into muscle tissue and releases predictably based on the depot. Oral undecanoate absorbs through the lymphatic system in amounts that vary with meal composition and individual GI physiology. Those two absorption profiles are fundamentally different in how they behave.
Getting levels to a stable therapeutic range with oral TU takes several weeks after the switch, and labs at approximately four to six weeks confirm whether the approach is working. Adjustments follow from those results. A licensed provider determines the starting protocol after reviewing your intake.
Patients also switch in the opposite direction. Those who find the multiple-daily-dose schedule of oral undecanoate difficult to maintain consistently sometimes return to injectable therapy. The same labs-guided approach applies in both directions.
More detail on how the pharmacokinetics of long-acting and oral undecanoate differ, and what that means for transitions between forms, is available in the guide on the long-acting and oral undecanoate pharmacokinetics.
What a provider weighs when choosing between forms
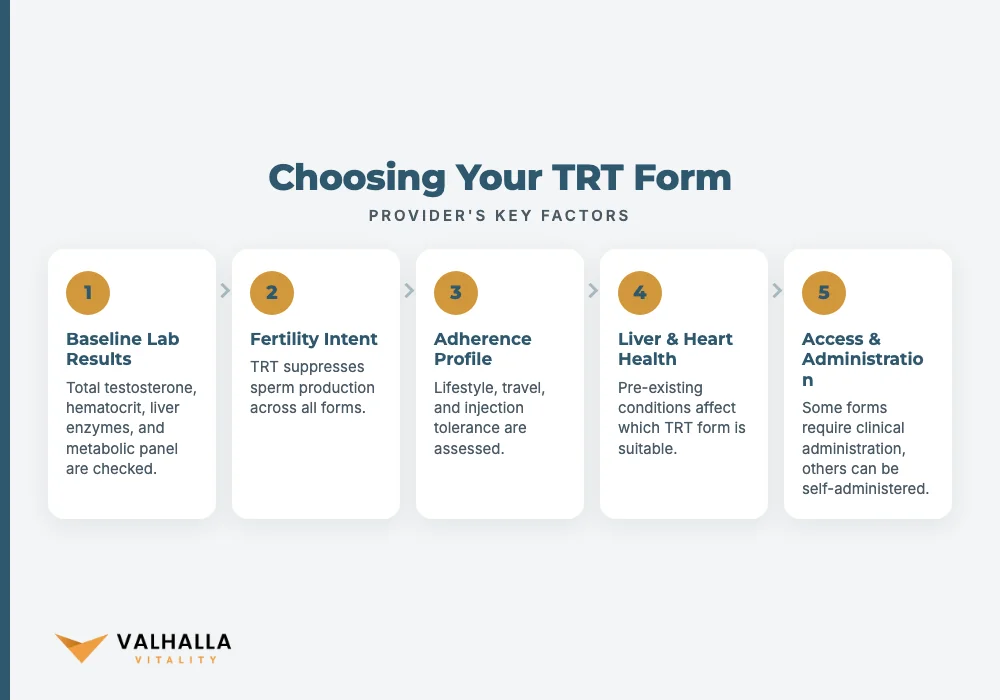
Selecting between testosterone undecanoate vs cypionate is not a preference call alone. Several clinical factors shape the decision.
Baseline labs: Total testosterone, hematocrit, liver enzymes, and a metabolic panel all inform which form is appropriate. Borderline-elevated hematocrit at baseline may point a provider away from high-peak injectable protocols. Pre-existing liver enzyme elevation may rule out oral undecanoate as a starting point.
Fertility intent: TRT suppresses sperm production through all routes. Naelitz et al. (2025) confirmed this consistently across testosterone therapy forms in reproductive-age men. Men who want to conceive need a direct discussion about alternatives before starting any TRT. This is not a minor footnote. It is a significant clinical consideration.
Adherence profile: Long-acting injectable undecanoate minimizes the injection burden once loading is established. Oral undecanoate requires multi-dose daily adherence with consistent food pairing. Testosterone cypionate falls between the two. Providers assess lifestyle, travel patterns, and injection tolerance as part of the intake evaluation.
Liver and cardiovascular health: Pre-existing liver disease affects oral TU candidacy. Cardiopulmonary conditions affect injectable TU candidacy given the documented POME risk. A complete health history review is standard before any testosterone therapy begins.
Access and administration context: FDA requirements for injectable testosterone undecanoate mean it is administered clinically, not at home. Oral testosterone undecanoate and cypionate can be self-administered. This affects which form is practically accessible based on a patient's location and telehealth setup. Availability varies by state.
For those weighing undecanoate against enanthate, another injectable ester common in some protocols, our comparison of undecanoate and enanthate as TRT options covers how the pharmacokinetic differences between these two long-chain esters affect practical prescribing decisions.
Ready to review your options with a licensed provider?
Book Your Consultation to discuss which testosterone form fits your labs, health history, and lifestyle.
FAQ
Is testosterone undecanoate better than cypionate for TRT?
Neither is universally better. Undecanoate offers fewer injections and a needle-free oral form; cypionate delivers faster early symptom relief and allows closer protocol monitoring between doses. A licensed provider evaluates your labs and health history to determine which form is appropriate for you.
How often do you need to inject testosterone cypionate?
Testosterone cypionate is typically injected every one to two weeks, though some providers prefer more frequent shorter-interval protocols to reduce level fluctuations. A licensed provider sets the schedule based on your lab results and how your body responds to treatment.
Can you switch from injectable to oral testosterone?
Yes, but the transition requires medical supervision and a new dose-finding period confirmed by labs. Oral testosterone undecanoate has different absorption dynamics than injectable cypionate, so stable levels need to be re-established and verified with follow-up testing before the new protocol is considered settled.
What are the side effects of testosterone undecanoate?
Oral undecanoate may cause nausea and stomach discomfort and requires liver enzyme monitoring throughout treatment. Injectable undecanoate carries a small risk of pulmonary oil microembolism (POME) and is administered in a clinical setting for this reason. Both forms may raise hematocrit and suppress sperm production.
Which testosterone form has fewer injection site reactions?
Oral testosterone undecanoate involves no injection site reactions since no injection is required. Both testosterone cypionate and injectable testosterone undecanoate can cause local soreness, redness, or bruising, with injectable undecanoate's larger injection volume sometimes producing more pronounced discomfort at the injection site.
Sources
- Goldstein I et al. (2025). Newer formulations of oral testosterone undecanoate: development and liver side effects. Sexual medicine reviews. PubMed
- Wang C et al. (2022). Testosterone Replacement Therapy in Hypogonadal Men. Endocrinology and metabolism clinics of North America. PubMed
- Adam JA et al. (2023). Occurrence of pulmonary oil microembolism (POME) with intramuscular testosterone undecanoate injection: literature review. International journal of impotence research. PubMed
- Nackeeran S et al. (2022). The Effect of Route of Testosterone on Changes in Hematocrit: A Systematic Review and Bayesian Network Meta-Analysis of Randomized Trials. The Journal of urology. PubMed
- Naelitz BD et al. (2025). Testosterone replacement therapy and spermatogenesis in reproductive age men. Nature reviews. Urology. PubMed
You May Also Like
 Oral Testosterone Undecanoate
Testosterone Decanoate vs Undecanoate: Key Differences
Testosterone decanoate vs undecanoate: compare half-life, injection frequency, and oral absorption to choose the right TRT ester for your needs.
October 7, 2026 ETRead more → Oral Testosterone Undecanoate
Testosterone Undecanoate Oral Dosage: Complete TRT Guide
Testosterone undecanoate oral dosage is set by a licensed provider after lab review. Understand oral TRT protocol, Kyzatrex dosage, and key dosing factors.
October 7, 2026 ETRead more → Oral Testosterone Undecanoate
Testosterone Undecanoate vs Enanthate: TRT Comparison
Testosterone undecanoate vs enanthate: compare injection schedules, the oral option, and how a licensed provider selects your TRT formulation.
October 6, 2026 ETRead more →