Secondary Hypogonadism: Causes, Symptoms, Treatment

The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Secondary hypogonadism is a condition in which testosterone levels fall not because the testes have failed, but because the hypothalamus or pituitary gland fails to send adequate signals to drive their production. It has become increasingly common, and it now accounts for the majority of cases of low testosterone in young men. For many men, tracing the problem to its upstream source is what makes effective treatment possible and, in some cases, what allows normal hormonal function to return.
What is the difference between primary and secondary hypogonadism?
Hypogonadism describes chronically low testosterone production, but the two forms differ fundamentally in origin. That difference determines every step from lab work to treatment selection.
Primary hypogonadism is a failure at the level of the testes. The gonads cannot produce adequate testosterone even when the hypothalamic-pituitary axis is functioning and delivering normal stimulatory signals. Genetic conditions, testicular injury, mumps orchitis, and prior chemotherapy or radiation are common structural causes. Lab findings show low testosterone alongside elevated LH and FSH, because the pituitary compensates by increasing its output in response to an unresponsive gland. A 2022 review in Best Practice & Research: Clinical Endocrinology & Metabolism noted that inherited forms of congenital central hypogonadism follow identifiable genetic patterns, and that separating these from acquired causes is relevant to both long-term management and counseling (Grinspon, 2022).
Secondary hypogonadism originates upstream. The hypothalamus releases insufficient gonadotropin-releasing hormone (GnRH), which in turn reduces the pituitary's output of luteinizing hormone (LH) and follicle-stimulating hormone (FSH). With less LH reaching the Leydig cells, testosterone production falls. With less FSH, sperm production also declines. The testes retain full structural capacity but receive inadequate instruction to produce testosterone. Labs show low or inappropriately normal LH and FSH alongside low testosterone. That is the inverse of the primary pattern.
It is also called central hypogonadism or hypogonadotropic hypogonadism. It is the more common form in adult men today, especially when driven by modifiable lifestyle and environmental factors rather than a structural brain lesion.
What causes secondary hypogonadism in men?
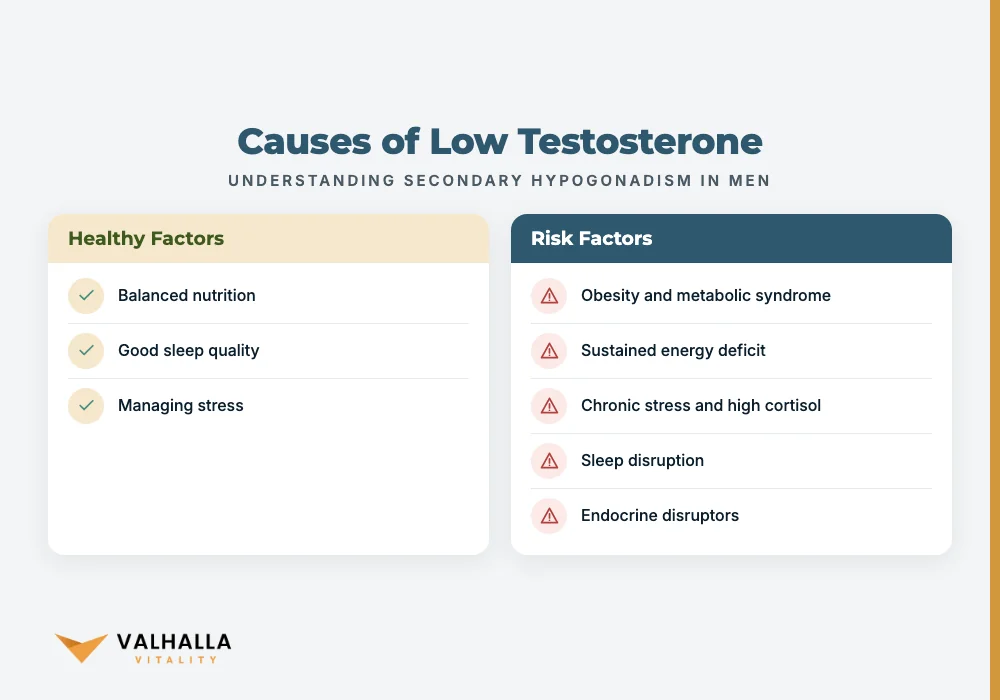
The condition has many overlapping testosterone deficiency causes, and modern life tends to apply several of them simultaneously. The hypothalamic-pituitary axis is sensitive to metabolic state, nutritional balance, stress hormones, sleep quality, and a growing range of environmental compounds. A 2010 review in the Journal of Advanced Pharmaceutical Technology & Research described how both structural and functional disruptions of central gonadal signaling converge on the same low-testosterone endpoint (Kumar et al., 2010).
The most commonly identified contributors include:
- Obesity and metabolic syndrome. Excess adipose tissue increases aromatase activity, converting testosterone to estradiol and amplifying negative feedback on hypothalamic GnRH output. A 2026 systematic review found that functional secondary hypogonadism is particularly prevalent in men with obesity, type 2 diabetes, or metabolic syndrome, with hormonal and metabolic dysfunction reinforcing each other in both directions (Ntais et al., 2026).
- Sustained energy deficit. Severe caloric restriction, prolonged fasting, or excessive training volume can suppress the HPG axis independently of body weight. This mechanism is clinically documented as fully reversible in some cases (Wong et al., 2019).
- Chronic stress and elevated cortisol. Cortisol directly suppresses GnRH release at the hypothalamic level. Men under persistent occupational, psychological, or physical stress show measurably reduced testosterone as a direct result.
- Sleep disruption. Testosterone rises during deep sleep and peaks in early morning. Short sleep duration, fragmented sleep, and shift work are each independently associated with lower androgen output.
- Endocrine disruptors and xenoestrogens. Compounds such as bisphenol A (BPA), parabens, and phthalates interfere with receptor signaling throughout the HPG axis. The National Institute of Environmental Health Sciences identifies endocrine disruptors hormones as documented reproductive axis disruptors, present in food packaging, personal-care products, and many household cleaners (NIEHS, 2022).
- Sedentary lifestyle. Physical inactivity suppresses androgen levels through mechanisms that are at least partially independent of obesity, though the two compound each other over time.
- Medications. Opioids are the most potent pharmacological suppressors of the HPG axis, and long-term use produces a recognized syndrome of opioid-induced androgen deficiency. Glucocorticoids, some antidepressants, and certain antifungals also suppress gonadotropin secretion to varying degrees.
- Hyperprolactinemia. A pituitary adenoma can elevate prolactin, which directly suppresses GnRH release. This structural cause requires its own dedicated evaluation and is distinct from functional secondary hypogonadism.
A broader trend amplifies the concern. A large population-based analysis published in Reproductive Biology and Endocrinology documented a significant downward drift in testosterone levels across successive birth cohorts, independent of aging (Chodick et al., 2020). That cohort-level shift reflects population-wide environmental and lifestyle pressures and helps explain the documented rise in low testosterone among young men, a pattern increasingly observed in men in their thirties, not only in older adults.
Reducing single-use plastic exposure and reviewing ingredients in personal-care products are practical steps that providers often mention alongside medical treatment. They support the overall picture but rarely resolve hypogonadism on their own.
What are the symptoms of secondary hypogonadism?
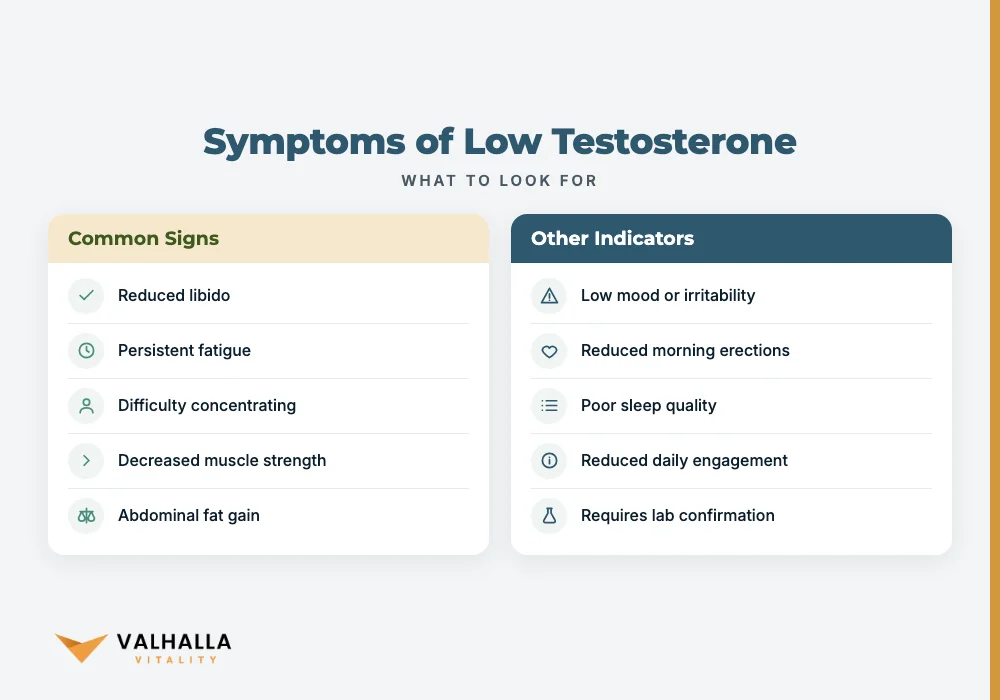
Central hypogonadism symptoms develop gradually. That slow onset is part of why men often normalize them for years before seeking evaluation.
The symptom spectrum is wide because testosterone affects neurological, metabolic, sexual, and musculoskeletal function simultaneously. Men with this hormonal pattern often report:
- Reduced or absent libido, or a clear decline from their prior baseline
- Persistent fatigue not explained by sleep deprivation or workload
- Difficulty concentrating, mental fog, or slower cognitive processing
- Reduced or absent morning erections
- Decreased muscle strength and slower recovery from exercise
- Gradual accumulation of abdominal fat alongside loss of lean mass
- Low mood, irritability, or depressive episodes without an obvious external cause
- Reduced drive and general engagement with daily activities
- Poor sleep quality even with sufficient sleep duration
These symptoms overlap significantly with depression, thyroid dysfunction, obstructive sleep apnea, and chronic fatigue. A 2004 review in Reviews in Urology emphasized that clinical assessment alone cannot distinguish hypogonadism from these conditions and that laboratory confirmation is essential for any accurate determination (Carnegie, 2004).
The symptom burden also does not map reliably to the testosterone level. Some men with moderately reduced levels report significant functional impairment. Others with similar lab values report little. A licensed provider evaluates both the laboratory findings and the full clinical picture before any assessment is made.
The risks of leaving secondary hypogonadism untreated
Left unaddressed, the condition does not plateau at a manageable inconvenience. The metabolic and structural consequences accumulate over time.
Low testosterone promotes visceral fat accumulation and impairs insulin sensitivity. The 2026 systematic review by Ntais et al. found that men with functional secondary hypogonadism and concurrent metabolic syndrome showed progressive worsening of metabolic markers when the hormonal component went unaddressed. The same review documented that appropriate treatment was associated with meaningful improvements in body composition, waist circumference, and glycemic control.
Bone mineral density is a slower-moving but real concern. Testosterone supports bone density in men, and prolonged low levels raise fracture risk in a process that unfolds quietly over years before becoming apparent on imaging.
Fertility deserves separate attention. Because this condition suppresses both LH and FSH, sperm production falls alongside testosterone. Extended untreated hypogonadism may reduce sperm counts to levels that impair fertility, and recovery timelines after starting treatment vary considerably.
Depression, reduced motivation, and social withdrawal are direct consequences of HPG axis disruption. They are also treatable, which gives men a concrete reason to pursue evaluation rather than continuing to work around the symptoms.
How is secondary hypogonadism treated?

Treatment options work at different levels of the HPG axis. The central principle is that the testes in this condition retain the capacity to produce testosterone. Treatment either restores the upstream signaling that should drive that production, or supplements testosterone directly in cases where axis stimulation is insufficient.
Clomiphene for low T and enclomiphene citrate therapy
Clomiphene citrate is a selective estrogen receptor modulator that blocks estrogen receptors at the hypothalamus. This reduces the negative feedback estrogen normally exerts on GnRH secretion. With that feedback reduced, GnRH pulses increase, the pituitary releases more LH and FSH, and the testes are driven to produce more testosterone. Clomiphene for low T preserves the full HPG axis. Sperm production is maintained rather than suppressed.
Enclomiphene citrate therapy uses only the active trans-isomer of clomiphene and has been studied specifically for secondary hypogonadism. A 2016 review in Endocrine Development described the pharmacological rationale for enclomiphene and related axis-stimulating compounds in hypogonadotropic hypogonadism, noting that agents preserving upstream signaling maintain testicular function and fertility potential in ways testosterone replacement cannot match (Rastrelli et al., 2016). A 2024 systematic review and meta-analysis in Andrology confirmed that estrogen-modulating agents in men with secondary hypogonadism significantly improved semen parameters, with consistent effects across studies (de Silva et al., 2024). Men evaluating this approach against direct testosterone replacement can find a detailed comparison at enclomiphene vs TRT: which therapy fits your goals.
A licensed provider determines the appropriate agent and dose after reviewing lab work, symptom history, and fertility intentions.
HCG and gonadorelin
Human chorionic gonadotropin (HCG) mimics LH. It binds directly to the Leydig cell receptor and stimulates testosterone synthesis, bypassing the hypothalamus and pituitary entirely. This makes HCG useful when the defect lies at the gonadotropin secretion level, and it also preserves testicular volume, which testosterone replacement does not.
Gonadorelin is a synthetic GnRH. Delivered in a pulsatile pattern that mimics physiological secretion, it stimulates the pituitary to release both LH and FSH. A 2022 review in Endocrine Reviews found that pulsatile GnRH administration achieves highly physiological HPG axis stimulation and is particularly suited to men whose defect originates at or above the hypothalamic level (Federici et al., 2022). The fertility outcomes with this approach are among the strongest documented for any treatment modality for this hormonal condition.
Testosterone replacement
For men who are not concerned with fertility, or for whom axis-stimulating approaches have not produced adequate response, direct testosterone replacement is a recognized option. The 2026 systematic review by Ntais et al. found that TRT produced significant improvements in body composition, glycemic control, and cardiovascular risk markers in men with secondary hypogonadism and metabolic syndrome.
However, exogenous testosterone suppresses endogenous LH and FSH through negative feedback. Sperm production falls or stops for as long as treatment continues. This suppression may persist for months after stopping and may not fully resolve. That is not a trivial trade-off. A licensed provider discusses it explicitly before any prescription is written.
Can secondary hypogonadism improve or normalize?
The answer depends on what is driving it. Recovery is possible. It is not universal.
Functional secondary hypogonadism caused by modifiable factors, such as obesity, energy deficit, sleep disruption, or medication use, may fully normalize when those factors are corrected. A 2019 report in Clinical Endocrinology documented men who developed hypogonadotropic hypogonadism purely from sustained energy deficit, through severe dietary restriction or high training volume, and who recovered complete normalization of LH, FSH, and testosterone after restoring caloric intake and reducing training load, without any pharmacological treatment (Wong et al., 2019). That demonstrates the HPG axis can recover fully when the suppressive factor is removed.
Obesity-related functional secondary hypogonadism follows a similar pattern. Significant fat loss can partially or fully restore hypothalamic GnRH output in men whose suppression was driven primarily by excess aromatization. The degree of recovery tends to track with the extent of weight loss and the duration of prior suppression before treatment began.
Full recovery is not always possible. Men with structural causes, such as a prolactinoma or a genetic GnRH deficiency, men with prolonged suppression, and men with multiple contributing factors may not recover sufficient HPG axis function through lifestyle change alone. Many require ongoing management.
The practical implication: identifying whether the cause is functional or structural is not a diagnostic formality. It determines whether restoring native function is a realistic goal or whether long-term hormonal management is the more accurate frame for treatment.
What providers evaluate before recommending a treatment path
Understanding this process helps men approach their first evaluation with clearer expectations.
Confirming the diagnosis requires more than a single low testosterone result. A complete hormonal panel typically includes total testosterone, free testosterone, LH, FSH, sex hormone-binding globulin (SHBG), estradiol, prolactin, and often thyroid function. Low or inappropriately normal LH and FSH alongside low testosterone confirm that the origin is central. Elevated prolactin raises concern for a pituitary adenoma and typically requires dedicated imaging before treatment decisions are made.
Beyond the panel, the provider distinguishes functional from structural causes. A man with obesity-driven functional suppression and a recent energy surplus has a fundamentally different clinical picture, and a different prognosis, than a man with a pituitary lesion or a hereditary GnRH deficiency. This distinction shapes both the choice of treatment and realistic expectations for how long management will be needed.
Fertility intentions are discussed explicitly and early. Clomiphene, enclomiphene citrate, HCG, and gonadorelin all preserve or may improve sperm production. Testosterone replacement suppresses it. A man who wants biological children needs to understand this distinction before any prescription is written. For a detailed overview of what a provider-led evaluation looks like for one of the commonly used axis-stimulating options, this resource on enclomiphene for low testosterone covers the clinical specifics in depth.
Metabolic health is part of the evaluation, not separate from it. As the 2026 review by Ntais et al. documented, men with secondary hypogonadism and metabolic syndrome require attention to both the hormonal and metabolic dimensions, since addressing only one tends to yield incomplete results.
Follow-up labs are built into the protocol from the start. Testosterone levels, hematocrit, estradiol, and related markers are monitored at regular intervals to confirm the treatment is working and to identify any adjustments needed. At Valhalla Vitality, provider review of intake happens within 24 business hours, with prescriptions directed to a partner US compounding pharmacy after approval. Availability varies by state.
Take the next step
If these symptoms or contributing factors sound relevant, a provider-led evaluation is the right starting point. Book Your Consultation to connect with a licensed clinician who can review your labs and health history.
FAQ
What causes secondary hypogonadism in men?
Secondary hypogonadism results from insufficient LH and FSH signaling from the hypothalamus or pituitary, not from a defect in the testes themselves. Common causes include obesity, chronic stress, sleep disruption, sustained energy deficit, long-term use of opioids or glucocorticoids, and exposure to endocrine-disrupting compounds such as BPA and parabens.
How is secondary hypogonadism treated?
Treatment typically involves either axis-stimulating agents that restore the body's own testosterone production, such as clomiphene citrate, enclomiphene citrate, HCG, or gonadorelin, or direct testosterone replacement for men who do not have fertility goals. A licensed provider determines the appropriate approach after reviewing lab results, symptom history, and fertility intentions.
Can secondary hypogonadism improve or normalize?
In some men, yes. Functional secondary hypogonadism caused by obesity, energy deficit, or medication use may normalize when the underlying factor is corrected. However, improvement depends on the cause and how long suppression was present, and many men require ongoing medical management alongside any lifestyle changes.
What is the difference between primary and secondary hypogonadism?
Primary hypogonadism is a failure of the testes themselves, producing low testosterone despite normal or elevated gonadotropin signaling. Secondary hypogonadism is a failure of the hypothalamus or pituitary to send adequate LH and FSH signals, leaving the testes understimulated. Laboratory gonadotropin levels distinguish the two.
What are the symptoms of secondary hypogonadism?
Common symptoms include low libido, persistent fatigue, difficulty concentrating, reduced muscle mass, increased abdominal fat, low mood, reduced motivation, and poor sleep quality. Because these symptoms overlap with depression, thyroid conditions, and other disorders, laboratory testing is a necessary part of any accurate evaluation.
Sources
- Ntais C et al. (2026). Metabolic Effects of Testosterone Replacement Therapy in Men with Functional Secondary Hypogonadism, Obesity and Type 2 Diabetes or Metabolic Syndrome: A Systematic Review. Medical sciences (Basel, Switzerland). PubMed
- Wong HK et al. (2019). Reversible male hypogonadotropic hypogonadism due to energy deficit. Clinical endocrinology. PubMed
- Grinspon RP (2022). Genetics of congenital central hypogonadism. Best practice & research. Clinical endocrinology & metabolism. PubMed
- Federici S et al. (2022). New and Consolidated Therapeutic Options for Pubertal Induction in Hypogonadism: In-depth Review of the Literature. Endocrine reviews. PubMed
- Rastrelli G et al. (2016). Different Medications for Hypogonadotropic Hypogonadism. Endocrine development. PubMed
- de Silva NL et al. (2024). Effect of oestrogen modulation on semen parameters in men with secondary hypogonadism: Systematic review and meta-analysis. Andrology. PubMed
- Chodick G et al. (2020). Secular trends in testosterone: findings from a large state-mandate care provider. Reproductive Biology and Endocrinology. https://doi.org/10.1186/s12958-020-00575-2
- Kumar P et al. (2010). Male hypogonadism: Symptoms and treatment. Journal of advanced pharmaceutical technology & research. https://doi.org/10.4103/0110-5558.72420
- Carnegie C (2004). Diagnosis of hypogonadism: clinical assessments and laboratory tests. Reviews in urology.
- National Institute of Environmental Health Sciences (2022). Endocrine disruptors. NIEHS
You May Also Like
 Featured, Testosterone
Enclomiphene vs TRT: Which Therapy Fits Your Goals?
Enclomiphene vs TRT compared: how each raises testosterone, which preserves fertility, and what labs a provider checks before recommending either.
September 25, 2026 ETRead more → Testosterone
OTC Testosterone Treatment Options for Men With Low T
OTC testosterone treatment: explore evidence-backed supplements, lifestyle strategies, and when a licensed provider review is the right next step.
September 26, 2026 ETRead more → Testosterone
TRT vs Enclomiphene: Which Therapy Fits Your Goals
TRT vs enclomiphene: understand how each low testosterone treatment works, who qualifies for each, and what a licensed provider assesses first.
September 26, 2026 ETRead more →