
The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Enclomiphene sperm count research shows that this oral SERM (selective estrogen receptor modulator) can raise sperm output by restoring the pituitary signals the testes need for active spermatogenesis. The mechanism is hormonal, not direct. Men with secondary hypogonadism, where the pituitary underproduces the gonadotropins that drive testicular function, may see meaningful changes in sperm parameters after treatment. A licensed provider determines whether the therapy is appropriate after reviewing labs and medical intake. If you are mapping your options, our dedicated guide on enclomiphene and male fertility walks through the clinical evidence in detail.
Enclomiphene sperm count: at a glance

Here is a practical snapshot of the reproductive parameters enclomiphene targets:
- LH (luteinizing hormone): rises after enclomiphene blocks estrogen feedback at the pituitary, signaling the testes to produce testosterone internally.
- FSH (follicle-stimulating hormone): rises alongside LH and directly activates Sertoli cells, which support and mature developing sperm inside the seminiferous tubules.
- Intratesticular testosterone: stays elevated because LH remains high, maintaining the local concentration sperm cells require to mature.
- Sperm count and concentration: clinical studies document increases in total sperm count with sustained enclomiphene therapy.
- Sperm motility and morphology: elevated testosterone in the testicular environment appears to improve sperm movement quality and shape, both of which influence fertilization.
- Ejaculate volume: some patients report modest changes, but enclomiphene ejaculate volume effects are a secondary outcome rather than a primary target.
This hormonal cascade is what separates enclomiphene from testosterone replacement. TRT adds testosterone from outside the body. Enclomiphene prompts internal production while keeping FSH active, so spermatogenesis continues.
Does enclomiphene increase sperm count?
Yes. Clinical evidence supports that enclomiphene can increase sperm count in men with secondary hypogonadism. A 2016 review by Rodriguez et al. in Expert Opinion on Pharmacotherapy found that enclomiphene citrate raised LH, FSH, and testosterone while preserving spermatogenesis, which is the opposite outcome produced by exogenous testosterone therapy. Research published in The Journal of Urology has documented improvements in sperm concentration and total motile sperm count, a measure of how many sperm in the ejaculate are both present and capable of fertilization, in men receiving enclomiphene treatment.
Secondary hypogonadism is the specific condition enclomiphene targets. The testes are capable of producing sperm. The problem is upstream. When the pituitary fails to send adequate gonadotropin signals, sperm production suffers even though the testes could respond if properly stimulated. This is the key distinction. Enclomiphene sperm count improvements depend on that upstream signal deficiency being the limiting factor. When the testes themselves are the primary source of the problem, stimulating gonadotropin output will not produce the same gains.
The core process works as follows. Enclomiphene blocks estrogen receptors at the hypothalamus and pituitary, removing the estrogen feedback that normally suppresses gonadotropin output. The pituitary responds by releasing more LH and FSH. Both hormones travel to the testes, where LH drives testosterone production and FSH activates the cells responsible for sperm development. For a detailed explanation of the molecular basis of this effect, see the mechanism and uses of enclomiphene citrate.
Enclomiphene sperm count outcomes are not identical across all men. Individual response depends on the underlying cause, baseline hormone levels, and treatment duration. A licensed provider tracks those variables through serial lab testing to assess whether the therapy is achieving the intended effect.
How does enclomiphene stimulate spermatogenesis?

Enclomiphene spermatogenesis effects run through two parallel hormone channels: FSH and intratesticular testosterone. Both are essential. When both rise together, the testes have the biological inputs they need to generate mature, motile sperm.
The FSH channel
FSH binds directly to Sertoli cells inside the seminiferous tubules. Sertoli cells physically support developing sperm and supply the nutrients required at each stage of maturation. When enclomiphene FSH levels rise, Sertoli cell activity increases, and more sperm cells can begin development and complete the full maturation sequence. Adequate FSH is also associated with improvements in sperm morphology. Well-formed cells with proper head, midpiece, and tail structure are more capable of fertilizing an egg than morphologically abnormal ones. Morphology is a core metric in semen analysis, so enclomiphene FSH levels that reach therapeutic range may contribute to quality improvements alongside count gains.
The testosterone channel
LH stimulates Leydig cells in the testes to produce testosterone. This testosterone stays concentrated inside the testes at levels far higher than what circulates in the blood. That local concentration is what spermatogenesis requires. The distinction between systemic and intratesticular testosterone matters clinically. Blood testosterone panels measure circulating levels. They do not capture the far higher concentrations that exist locally during active, gonadotropin-driven production.
Applied or injected testosterone suppresses LH production, which drops intratesticular testosterone to very low levels even when blood panels look normal. The difference is fundamental. Enclomiphene keeps LH elevated, preserving the local testosterone environment the testes need for sperm maturation.
The combined environment
Together, rising enclomiphene FSH levels and sustained intratesticular testosterone create conditions in the seminiferous tubules where spermatogenesis can proceed efficiently. The 2016 Rodriguez et al. review confirmed that enclomiphene achieved these hormonal changes while maintaining sperm production. That combined effect positions it as a meaningful low sperm count treatment option for men whose hypogonadism originates at the pituitary level.
How long does enclomiphene take to improve sperm count?
Sperm production is a biological cycle with a fixed minimum duration. It takes approximately 74 days for a sperm cell to progress from stem cell to mature gamete. Additional time is required for the cell to travel through the reproductive tract before it appears in a semen sample. No therapy shortens that biological clock.
Research shows that hormone markers, including LH, FSH, and testosterone, respond relatively quickly after starting enclomiphene. Semen analysis results lag behind because new sperm cells need the full maturation cycle before appearing in an ejaculate sample. Hormone panel changes may be visible after several weeks. Meaningful enclomiphene sperm count changes in a semen analysis take considerably longer.
Providers typically recheck hormone panels after several weeks and request repeat semen analyses at longer intervals to capture real change in sperm parameters. The exact monitoring schedule varies by individual. A licensed provider determines that schedule based on baseline labs and how results trend over time. Regular follow-up is what allows enclomiphene fertility outcomes to emerge across the months a complete spermatogenic cycle requires.
Because a meaningful enclomiphene sperm count response takes months to appear in semen parameters, starting treatment early in a fertility planning timeline gives the therapy room to work. Providers can set realistic expectations based on the biology involved and adjust the plan if hormone labs are not trending as expected.
Does enclomiphene affect ejaculate volume?
Ejaculate volume is one component of a complete semen analysis. Enclomiphene ejaculate volume effects are not a primary target of the therapy. Volume is largely determined by secretions from the seminal vesicles and prostate, not by sperm count or testosterone levels alone.
That said, testosterone does influence the secretory activity of those glands. When enclomiphene raises testosterone through the LH pathway, some men may notice modest changes in volume as a secondary effect. Clinical studies on enclomiphene have not reported volume as a consistent or significant primary outcome. A provider reviewing a complete semen analysis looks at all parameters together, and the meaning of any single value depends on the broader hormonal context.
Can enclomiphene treat male infertility?
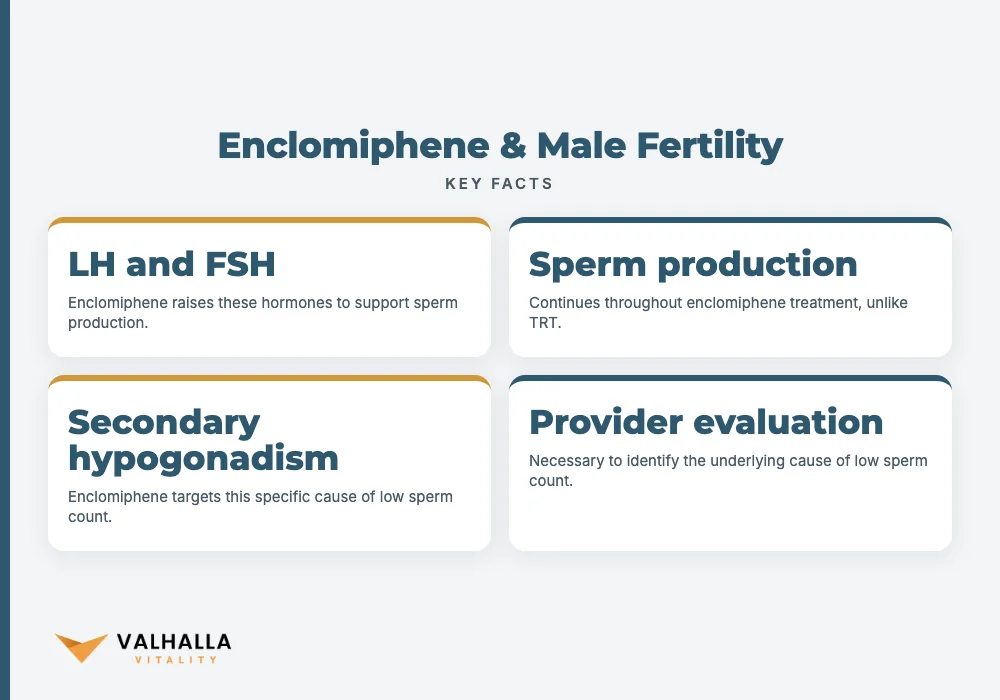
Enclomiphene male fertility outcomes depend on the underlying diagnosis. The therapy targets secondary hypogonadism, where impaired testicular function results from insufficient pituitary signaling rather than primary testicular failure. When inadequate LH and FSH output is driving a low sperm count, restoring those signals may produce meaningful improvements in enclomiphene sperm count results and fertility parameters broadly.
Not all low sperm count cases share the same hormonal profile. This is why a provider evaluation is the necessary starting point. Enclomiphene does not address primary testicular failure, chromosomal abnormalities, structural obstructions, or other non-hormonal causes of infertility. A semen analysis and full hormone panel identify whether secondary hypogonadism is the driving factor. Secondary hypogonadism itself can have contributing causes, including obesity, certain medications, or sleep disorders. Identifying those factors is part of the evaluation process.
Why enclomiphene preserves fertility while TRT does not
For men who want to address low testosterone symptoms without sacrificing fertility, enclomiphene has a clear advantage over exogenous testosterone replacement. TRT suppresses LH and FSH. Sperm production drops sharply within weeks of starting, often to zero. Enclomiphene does the opposite. It raises LH and FSH while allowing the testes to produce testosterone internally. Sperm production continues throughout treatment.
Some men whose fertility declined during TRT transition to enclomiphene under provider guidance to restore sperm production. The underlying principle is the same: restore gonadotropin-driven testicular function rather than replace it from outside. For more on how hormone balance intersects with fertility goals, see how enclomiphene addresses secondary hypogonadism and hormone balance.
What providers evaluate before prescribing
Before recommending enclomiphene, providers typically review:
- Serum testosterone (total and free), LH, and FSH at baseline
- Semen analysis covering count, concentration, motility, morphology, and volume
- Thyroid function and prolactin, to exclude other hormonal causes
- Health history, current medications, and reproductive goals
This evaluation confirms whether secondary hypogonadism is present and whether enclomiphene is an appropriate path. At Valhalla Vitality, a licensed provider determines the dose after labs, not before them.
Monitoring during treatment
Ongoing lab reviews are a standard part of enclomiphene therapy. Providers check hormone panels and request periodic semen analyses to track whether the treatment is producing the intended hormonal effect. Adjustments depend on how lab values trend over time. Providers also watch for potential side effects, such as mood changes or visual disturbances, so the plan can be adjusted if needed. For detail on what the monitoring process involves, see lab follow-up and parameter tracking during enclomiphene therapy.
Oral administration offers a practical adherence advantage over injectable therapies like hCG or gonadotropin injections. Consistent dosing supports the months-long timelines that spermatogenesis improvements require.
Ready to explore your options?
A licensed provider can review your intake and determine whether enclomiphene is appropriate for your situation when you Book Your Consultation.
FAQ
Does enclomiphene increase sperm count?
Yes, clinical evidence shows enclomiphene can increase sperm count in men with secondary hypogonadism. It raises LH and FSH, which together drive intratesticular testosterone and Sertoli cell activity, both required for spermatogenesis. Individual results depend on the underlying cause and are tracked through repeat lab testing.
How long does enclomiphene take to improve sperm count?
Because sperm maturation takes approximately 74 days biologically, meaningful changes in sperm parameters typically appear after several months of treatment. Hormone levels respond sooner than semen analysis results. A provider sets the monitoring schedule based on baseline labs and how hormone panels trend over time.
Is enclomiphene a low sperm count treatment option?
Enclomiphene is a low sperm count treatment option for men with secondary hypogonadism, where insufficient pituitary signaling is the root cause. It is not appropriate for primary testicular failure or non-hormonal causes of infertility. A full diagnostic evaluation determines whether the hormonal profile fits.
Does enclomiphene affect ejaculate volume?
Enclomiphene ejaculate volume effects are not a primary outcome of the therapy. Some men may notice modest changes because testosterone influences accessory gland secretions, but clinical studies have not identified volume as a consistent significant effect. A provider reviews all semen analysis parameters together rather than volume in isolation.
Can enclomiphene be used after testosterone replacement suppressed sperm production?
Some men whose sperm production declined on TRT transition to or add enclomiphene under provider guidance to restore fertility. Enclomiphene raises LH and FSH, restarting the signals TRT suppressed. A provider evaluates current hormone labs and semen analysis to determine whether the transition is appropriate and how to manage it safely.
Sources
- Rodriguez KM et al. (2016). Enclomiphene citrate for the treatment of secondary male hypogonadism. Expert Opinion on Pharmacotherapy. PubMed
You May Also Like
 Enclomiphene
 Hair Loss: DHT, Follicles, and the Evidence
Enclomiphene hair loss is not a listed side effect, but testosterone raises DHT, which can affect follicles. Here is what clinical research shows.
October 12, 2026 ETRead more → Enclomiphene
 for Gyno: Causes, Prevention & Treatment
Enclomiphene for gyno: how this SERM may help reduce gynecomastia by rebalancing estrogen and testosterone levels. Talk to a licensed provider today.
October 11, 2026 ETRead more → Enclomiphene
 vs Tamoxifen for PCT and Testosterone
Enclomiphene vs tamoxifen: compare how each SERM supports testosterone recovery, PCT protocols, and side effect profiles before talking to a provider.
October 11, 2026 ETRead more →