
The following blog post is for entertainment and informational purposes only. It is not intended to provide medical advice or diagnosis. Please consult your doctor before making any health-related decisions.
Enclomiphene vs tamoxifen is the comparison men most often face when evaluating SERM post cycle therapy options: both are selective estrogen receptor modulators that restart natural testosterone production by acting on the hypothalamic-pituitary axis, but their receptor selectivity, clinical evidence, and risk profiles differ meaningfully. For a focused look at how this plays out when tamoxifen is marketed under its Nolvadex brand name, the enclomiphene vs Nolvadex comparison for hormonal balance covers that overlap directly. A licensed provider reviews current labs and individual history before recommending either compound.
| Enclomiphene | Tamoxifen (Nolvadex) | |
|---|---|---|
| Primary target | Hypothalamic estrogen receptors | Pituitary and breast-tissue estrogen receptors |
| Testosterone mechanism | Raises LH and FSH, stimulating testicular production | Reduces estrogen negative feedback, indirectly raising T |
| Fertility impact | May preserve or improve sperm production | Limited male fertility data |
| Visual risk | Not documented in trials | Retinopathy at cumulative exposure |
| PCT role | Testosterone recovery, secondary hypogonadism | Gynecomastia control, HPG-axis restart |
Enclomiphene vs tamoxifen: how each SERM acts on the male HPG axis
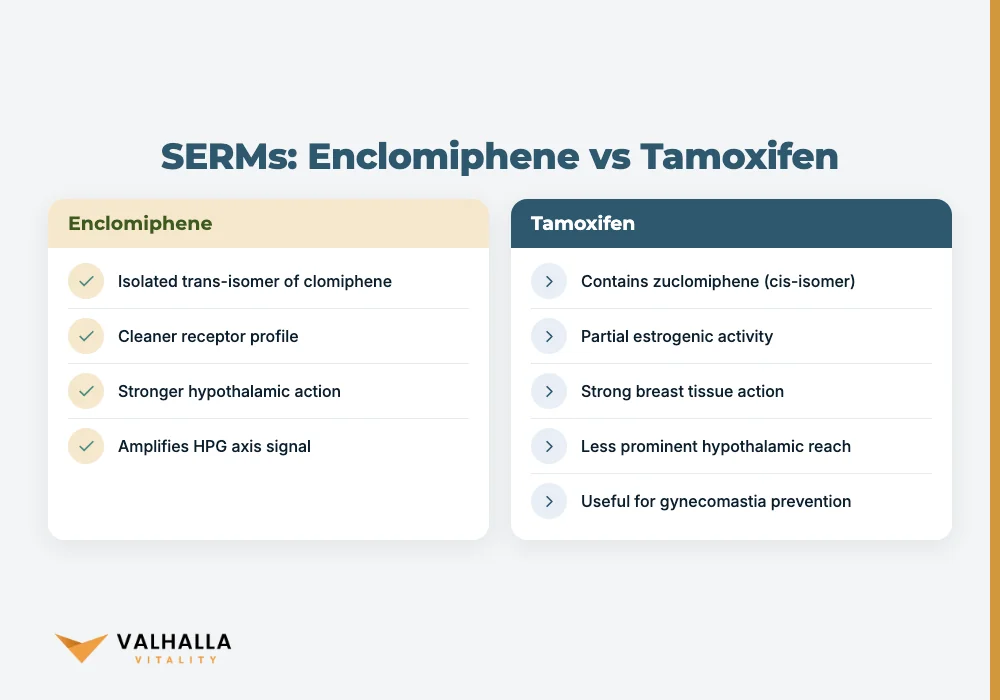
Both compounds interrupt the same negative feedback loop. The hypothalamus and pituitary monitor circulating estrogen to regulate gonadotropin-releasing hormone (GnRH), luteinizing hormone (LH), and follicle-stimulating hormone (FSH). When estrogen is elevated, the signal is dialed back. A SERM competes for those receptors, removing the brake. LH and FSH rise. The testes respond by producing more testosterone.
Enclomiphene is the isolated trans-isomer of clomiphene. The parent molecule also contains zuclomiphene, a cis-isomer with partial estrogenic activity that can blunt the same HPG-axis signal enclomiphene is trying to amplify. A 2016 review in Expert Opinion on Pharmacotherapy by Rodriguez KM et al. identified this cleaner receptor profile as the rationale for studying enclomiphene specifically in men with secondary hypogonadism.
The enclomiphene vs tamoxifen distinction at the receptor level shapes downstream outcomes. Tamoxifen blocks estrogen receptors strongly in breast tissue and, to a lesser degree, at the pituitary. In men, the breast-tissue action is what makes it useful for gynecomastia prevention. Its hypothalamic reach is less prominent than enclomiphene's, which affects how each compound drives long-term testosterone recovery.
Is enclomiphene better than tamoxifen for PCT?
No head-to-head male PCT trial has established clear superiority for either compound. A 2025 systematic review in Archives of Endocrinology and Metabolism by Hohl A et al. examined randomized controlled trials of clomiphene and enclomiphene in men with hypogonadism and confirmed that both classes raised serum testosterone and gonadotropin levels. Tamoxifen was not included as a comparator, so claims of categorical superiority lack direct clinical grounding.
Comparing enclomiphene to tamoxifen for testosterone recovery, the evidence suggests both raise T but through different leverage points. Enclomiphene for PCT concentrates the signal at the hypothalamus, producing a more direct LH/FSH drive. Tamoxifen PCT protocols add peripheral estrogen-receptor blockade, useful when gynecomastia prevention matters as much as testosterone recovery. Those goals frequently overlap in post-cycle scenarios, and that overlap guides which SERM a provider selects.
Questions about tamoxifen pct dosage or enclomiphene dosing are answered by a licensed provider after reviewing lab results and individual response, not from a fixed protocol.
What are the side effects of tamoxifen vs enclomiphene in men?
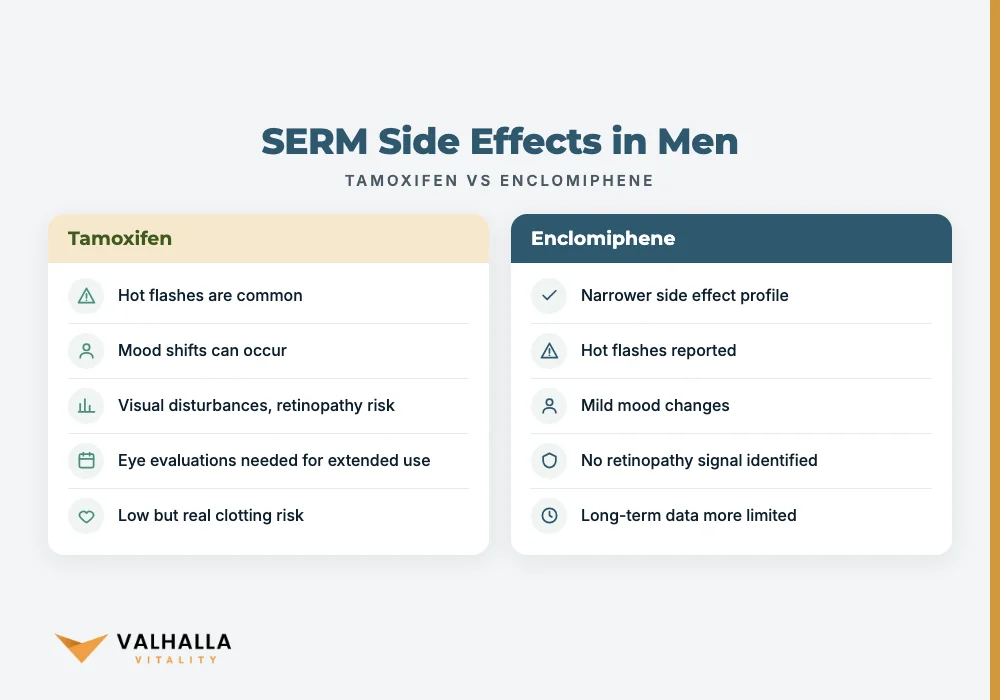
Tamoxifen side effects men report most often include hot flashes, mood shifts, and visual disturbances. The visual risk warrants attention. A 2024 comprehensive review in Survey of Ophthalmology by Tenney S et al. described tamoxifen retinopathy as a cumulative-exposure adverse effect with specific anatomical findings. A 2023 review in the same journal by Bazvand F et al. confirmed the association and noted the risk is not limited to high-dose users. Anyone on extended tamoxifen therapy should have baseline and follow-up eye evaluations.
Enclomiphene's side effect profile is narrower. The enclomiphene clinical evidence summary reviews tolerability data from available trials; the Rodriguez KM et al. (2016) analysis noted hot flashes and mild mood changes as the main complaints, with no retinopathy signal identified. Removing zuclomiphene's estrogenic activity also addresses one variable associated with older, less selective SERMs.
Tamoxifen also carries a low but real thromboembolic risk. Men with pre-existing clotting factors need individualized assessment before starting.
Which SERM is safer for men: enclomiphene or tamoxifen?
When weighing enclomiphene vs tamoxifen, the ophthalmological data most often tips the risk discussion. Enclomiphene carries a narrower adverse-effect profile in men based on current published evidence. The retinopathy risk documented by Tenney S et al. (2024) and Bazvand F et al. (2023) is specific to tamoxifen, with no equivalent signal in enclomiphene trials. That does not make enclomiphene risk-free: hot flashes and mood effects occur, and long-term data remain more limited than for tamoxifen. A provider weighs those specifics against individual history.
Can enclomiphene replace Nolvadex after a steroid cycle?
Nolvadex is a brand name for tamoxifen. Whether enclomiphene can replace it depends on the clinical goal. Enclomiphene testosterone recovery data from secondary hypogonadism trials show consistent restoration of serum testosterone into physiological ranges. It does not provide the same direct estrogen-receptor blockade at breast tissue that tamoxifen delivers for gynecomastia prevention.
Some providers use both. Enclomiphene drives LH/FSH output; tamoxifen manages peripheral estrogen effects. Others use one compound based on which clinical problem is more pressing. Men who want to preserve fertility during recovery have a specific reason to discuss enclomiphene with their provider: the LH/FSH mechanism maintains testicular function in a way that exogenous testosterone does not. For more on that contrast, see how enclomiphene compares to testosterone injection therapy as a clinical recovery option.
The enclomiphene vs nolvadex question ultimately comes down to mechanism: one compound restarts the HPG axis from the top, the other blocks estrogen signaling at the periphery. A provider's review determines which angle the situation calls for.
Talk to a licensed provider
If you are weighing enclomiphene vs tamoxifen and want a personalized assessment, Book Your Consultation to have a licensed clinician review your labs and history.
FAQ
Is tamoxifen or enclomiphene more commonly used for PCT?
Tamoxifen has been part of PCT protocols for decades, primarily for gynecomastia prevention and HPG-axis effects. Enclomiphene is a newer compound gaining clinical use in secondary hypogonadism treatment. A licensed provider determines which is appropriate after reviewing labs and the specific recovery goals.
Does enclomiphene affect sperm production differently than tamoxifen?
Enclomiphene raises LH and FSH directly, stimulating both testosterone synthesis and sperm production in the testes. Tamoxifen's mechanism is less focused on gonadotropin output. Men who want to preserve fertility during hormonal recovery often discuss enclomiphene with their provider for that reason.
Why does tamoxifen carry a retinopathy risk that enclomiphene does not?
Tamoxifen accumulates in retinal tissue, producing dose-dependent changes confirmed in two independent reviews in Survey of Ophthalmology (Tenney S et al., 2024; Bazvand F et al., 2023). Enclomiphene does not share this mechanism or this documented risk. Regular eye monitoring is recommended for anyone on extended tamoxifen use.
Can a provider prescribe enclomiphene and tamoxifen together?
Some providers use combination SERM protocols when the clinical picture calls for both HPG-axis stimulation and peripheral estrogen control. This approach requires individual assessment, ongoing labs, and provider monitoring. A licensed provider determines whether a combination is appropriate after reviewing your intake.
Sources
- Hohl A et al. (2025). Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Archives of Endocrinology and Metabolism. PubMed
- Rodriguez KM et al. (2016). Enclomiphene citrate for the treatment of secondary male hypogonadism. Expert Opinion on Pharmacotherapy. PubMed
- Tenney S et al. (2024). Tamoxifen retinopathy: A comprehensive review. Survey of Ophthalmology. PubMed
- Bazvand F et al. (2023). Tamoxifen retinopathy. Survey of Ophthalmology. PubMed
You May Also Like
 Enclomiphene
 Hair Loss: DHT, Follicles, and the Evidence
Enclomiphene hair loss is not a listed side effect, but testosterone raises DHT, which can affect follicles. Here is what clinical research shows.
October 12, 2026 ETRead more → Enclomiphene
 for Gyno: Causes, Prevention & Treatment
Enclomiphene for gyno: how this SERM may help reduce gynecomastia by rebalancing estrogen and testosterone levels. Talk to a licensed provider today.
October 11, 2026 ETRead more → Enclomiphene
 Heart Palpitations: What Men Need to Know
Enclomiphene heart palpitations occur in some men on therapy. Learn how the drug affects blood pressure, cholesterol levels, and cardiovascular risk.
October 11, 2026 ETRead more →